About this course:
This module explores the epidemiology, pathophysiology, risk factors, clinical manifestations, diagnosis, and treatment modalities of pancreatic cancer to help clinicians provide optimal care, patient education, and support throughout the disease trajectory.
Course preview
Pancreatic Cancer
This module explores the epidemiology, pathophysiology, risk factors, clinical manifestations, diagnosis, and treatment modalities of pancreatic cancer to help clinicians provide optimal care, patient education, and support throughout the disease trajectory.
By the completion of this module, learners will be able to:
- discuss the epidemiology of pancreatic cancer in the United States and risk factors for the development of the disease
- examine the anatomy of the pancreas and the pathophysiology leading to the development of pancreatic cancer
- discuss the signs and symptoms, diagnostic workup, pancreatic cancer subtypes, and components of pancreatic cancer staging
- review the evidence-based guidelines for the management of pancreatic cancer, including treatment side effects, risks, and the elements of patient education
Cancer remains a global health problem, and it is the second leading cause of death in the United States among people under the age of 85. Although cancer mortality has declined over the last few decades, certain types of cancer remain challenging to diagnose and treat. According to the American Cancer Society (ACS), approximately 67,530 people (35,190 males and 32,340 females) in the United States will be diagnosed with pancreatic cancer, and about 52,740 (27,230 males and 25,510 females) will die annually. This accounts for 3.2% of all new cancer diagnoses and 8.4% of all cancer deaths. Pancreatic cancer is one of the most challenging cancers to diagnose, as it shows little or no symptoms during the early stages, and there are no effective screening tests. Given its poor prognosis, healthcare providers (HCPs) must remain updated and informed on the clinical features of the disease, as well as its pertinent risk factors, to facilitate a timely diagnosis and reduce mortality (ACS, 2026a; Siegel et al., 2026; Surveillance, Epidemiology, and End Results [SEER] Program, 2026).
Epidemiology
The average lifetime risk for developing pancreatic cancer among the general population is approximately 1.7% (1 in 56 for males and 1 in 60 for females) in the United States. Based on data from the SEER Program, the median age at diagnosis is 71. It is most frequently diagnosed in individuals aged 65 to 74 (32.7%), followed by those aged 75 to 84 (25.9%). The condition is more common among males (13.9 per 100,000) than females (11.3 per 100,000). Incidence rates are highest for Black males (18.0 per 100,000), followed by White males (16.3 per 100,000), Black females (15.4 per 100,000), Indigenous males (13.4 per 100,000), and Hispanic males (13.6 per 100,000). Asian/Pacific Islanders have the lowest incidence rates among males (11.5 per 100,000) and females (9.8 per 100,000). Mortality rates are highest among Black males and females, respectively (15.0 per 100,000 and 12.3 per 100,000). Mortality rates are lowest among Asian/Pacific Islander males and females, respectively (8.2 per 100,000 and 7.2 per 100,000). The 5-year survival rate for pancreatic cancer is poor and depends on the stage at diagnosis. Localized pancreatic cancer (i.e., cancer that has not spread outside of the pancreas) has a 5-year survival rate of 44%, which declines to only 17% for regional (i.e., cancer that has spread to nearby structures or lymph nodes) and 3% for those with distant metastases (i.e., cancer spreading to distant organs or sites outside the pancreas). Unfortunately, roughly 80% of pancreatic cancers are diagnosed at an advanced stage, accounting for the poor survival rates. The median age at death is 73 years, with the highest percentage of deaths among those aged 65 to 74 (32.2%), followed by those aged 75 to 84 (29.6%; ACS, 2026a, 2026b; SEER Program, 2026).
Risk and Protective Factors
All individuals are at risk for pancreatic cancer, and the risk increases with age. Environmental factors, lifestyle choices, and genetic factors all play important roles in the development of the condition. Although most pancreatic cancers are diagnosed without identifiable risk factors or a family history, several influences can increase or decrease a person’s risk of pancreatic cancer. Table 1 describes the major risk and preventive factors (ACS, 2025d).
Table 1
Pancreatic Cancer Risk and Protective Factors
Factor | Description of Evidence |
Tobacco use | An estimated 25% of pancreatic cancers are linked to cigarette smoking, as individuals who smoke are twice as likely to be diagnosed with the disease as those who have never smoked. Cigar smoking and smokeless tobacco products also increase the risk. The American Cancer Society cites tobacco as the most important modifiable risk factor for pancreatic cancer. Avoiding tobacco and smoking cessation can lower the risk of pancreatic cancer. |
Advancing age | The risk of developing pancreatic cancer increases with age. Individuals are rarely diagnosed before the age of 45, and nearly two-thirds of all pancreatic cancers are diagnosed in individuals 65 and older. |
Biological sex | As noted earlier, males are...
...purchase below to continue the course |
Elevated body mass index (BMI) | Elevated BMI (30 or higher) is a risk factor for pancreatic cancer, as those with an elevated BMI are 20% more likely to develop the disease. Those who carry extra weight around their waistline, even without an elevated BMI, are also at risk. |
Race | Black individuals are more likely to develop pancreatic cancer than White individuals. The exact reason for this is not clear, but it may be due to the increased incidence of other risk factors such as smoking, elevated BMI, and diabetes. |
Pancreatitis | Pancreatitis is a condition characterized by pancreatic inflammation and is associated with an increased risk for pancreatic cancer. Chronic pancreatitis denotes long-term inflammation, is often seen in patients with heavy alcohol use, and carries a higher risk for pancreatic cancer. Excess alcohol use increases the risk of chronic pancreatitis, heightening the risk of pancreatic cancer. Avoiding alcohol or limiting intake to two drinks per day for males or one for females can lower the risk of pancreatitis. |
Type 2 diabetes mellitus (T2DM) | The relative risk of pancreatic cancer in people with T2DM for at least 5 years is double that of persons without T2DM; however, the etiology of this relationship remains unclear. It is indeterminate if patients with type 1 diabetes mellitus (T1DM) are at increased risk. |
Occupational exposures | Specific workplace exposures, such as the chemicals used for dry cleaning or metalworking industries, may increase pancreatic cancer risk. |
Diet | While data is not definitive, and additional studies are necessary, research suggests that processed foods, red meats, and excess sugar intake can increase pancreatic cancer risk. A healthy diet that includes adequate fruits, vegetables, and whole grains while limiting highly processed foods, sugars, and red meat is recommended as a preventative measure. Low serum levels of lycopene (a carotenoid found in fruits) and selenium have been found in patients who have pancreatic cancer, suggesting that fruit and selenium consumption are protective factors. |
Family history | Patients are at increased risk for pancreatic cancer if they have a first-degree relative (i.e., parent or sibling) with the disease. Approximately 10% of individuals with pancreatic cancer have a positive family history of the disease. In some families, the risk is due to a hereditary syndrome, whereas in other families, the increased risk remains unknown. Familial pancreatic cancer is defined as having two or more first-degree relatives affected with pancreatic cancer (refer to next section). |
(ACS, 2025d, 2026b; Cabebe, 2026a; Fernandez-del Castillo & Jimenez, 2026a)
Other risk factors have been identified in the literature, but the evidence supporting a link to pancreatic cancer is uncertain. For example, some studies have found an increased risk of pancreatic cancer with increased coffee consumption, whereas others have shown no increased risk. Similarly, studies have shown conflicting data on the association of pancreatic cancer with aspirin (Bayer) or other nonsteroidal anti-inflammatory drugs, Helicobacter pylori infection, hepatitis B infection, and hepatitis C infection. Some studies have also found that physical inactivity is a risk factor, whereas other studies have not shown this to be a factor (ACS, 2025d; Fernandez-del Castillo & Jimenez, 2026a; Puckett & Garfield, 2024).
Germline and Somatic Gene Mutations
Germline (inherited) and somatic (acquired) mutations in cancer-causing oncogenes and tumor suppressor genes are common in pancreatic cancer. Inherited (or hereditary) mutations are passed along familial lines directly from a parent to a child. These mutations are found in every body cell and increase the individual’s predisposition to developing pancreatic cancer. Unlike inherited mutations, somatic changes are not hereditary or passed to subsequent generations. Instead, somatic mutations appear during one’s lifetime due to environmental exposures, such as ultraviolet radiation from sun exposure, ionizing radiation, free radicals, carcinogens, or chemical exposures. Somatic mutations only occur in specific cells within the body. An oncogene is a mutation associated with cancer development. In their normal and nonmutated state, oncogenes are called proto-oncogenes, regulating healthy cell growth and division. When a proto-oncogene mutates into an oncogene, it becomes permanently activated (turned on), fueling unregulated cell growth and resultant cancer cells (Cabebe, 2026a; Norris, 2024; Puckett & Garfield, 2024).
Rat sarcoma (RAS) is a family of genes that includes Kirsten rat sarcoma (KRAS) and neuroblastoma rat sarcoma genes, which comprise the most frequently mutated oncogene family in cancer. KRAS, located on chromosome 12p, is cited as the most commonly activated oncogene in pancreatic cancer, present in more than 90% of pancreatic adenocarcinomas. The KRAS protein becomes permanently activated in these cases, inducing continual cellular proliferation, invasion, and survival. The KRAS mutations are found at the earliest stages of pancreatic cancer development, suggesting that they are an important factor for tumor initiation. Research has shown that while the KRAS drives tumor initiation, the acquisition of further mutations is required for progression. Given the prevalence of KRAS in early stages of pancreatic cancer, it has been a target for the development of early detection testing. Clinical research has also demonstrated that KRAS mutation correlates with a poorer prognosis in patients with pancreatic cancer (Bannoura et al., 2021; Hruban, 2026; Zhang et al., 2023).
Tumor suppressor genes are healthy genes that slow cell division, repair DNA errors, and induce apoptosis (programmed cell death). Under physiologic conditions, tumor suppressor genes regulate healthy cellular growth and division and prevent cells with mutated or damaged DNA from replicating, thereby avoiding tumor development. These processes continue unregulated when tumor suppressor genes are inactivated (turned off). Consequently, DNA damage accumulates in cells, which continue to divide uncontrollably, leading to tumor growth. The most common tumor suppressor gene affected in pancreatic cancer is the p16 gene, also known as cyclin-dependent kinase inhibitor 2A (CDKN2A). This gene is inactivated in about 95% of cases, and mutations occur in pancreatic cancer at a rate higher than in nearly any other tumor type. p16 is one of the inhibitors of cyclin-dependent kinases, or CDK enzymes, which drive a cell’s progression through the division cycle. Individuals with CDKN2A/p16 mutations have a 20% increased risk of developing pancreatic cancer by age 75. The second most common is the p53 (TP53) gene, which is inactivated in approximately 75% to 85% of pancreatic cancers. Since p53 is critical in regulating DNA repair and cell division, it is nicknamed the “guardian of the genome” (Cabebe, 2026a; Hruban, 2026; Mahon, 2025; Norris, 2024; Stefanoudakis et al., 2024).
Inherited Risk
Roughly 10% of pancreatic cancers are associated with inherited mutations in specific genes, and some of the most common genetic syndromes predisposing individuals to pancreatic cancer are described in this section (Canto, 2026; NCCN, 2026a).
Hereditary Pancreatitis (HP)
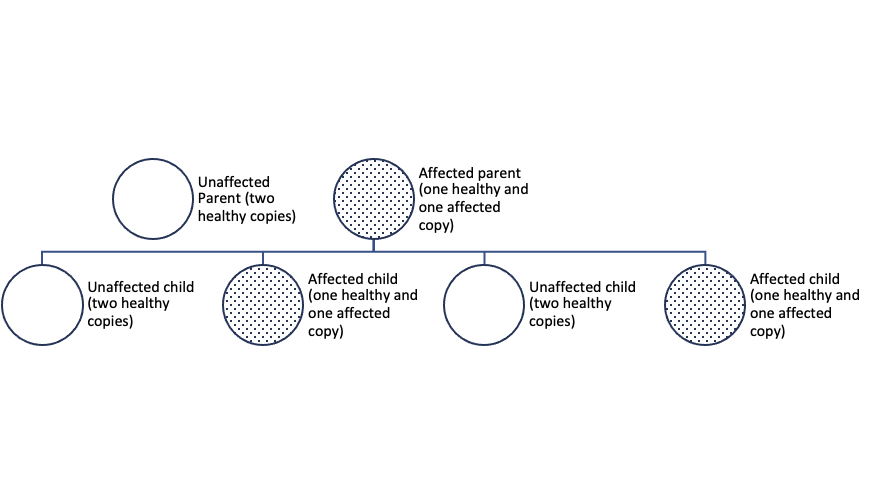
HP is a rare genetic syndrome characterized by recurring episodes of severe epigastric pain and hyperamylasemia (elevated serum amylase), with the first episode typically occurring before age 10. The condition is most commonly associated with a mutation in the protease serine 1 (PRSS1) gene, inherited in an autosomal dominant (AD) pattern. As demonstrated in Figure 1, in an AD inheritance pattern, a copy of the mutated gene in each cell is sufficient to increase the risk of developing cancer. The altered gene can be inherited from either parent, and each child of a parent with the mutation has a 50% chance of inheriting the same gene mutation. HP carries a risk of pancreatic cancer about 50 times higher than the general population. It is estimated that up to 80% of people with HP have mutations in the PRSS1 gene. PRSS1 provides instructions for cationic trypsinogen, an enzyme that aids food digestion. Cationic trypsinogen is generated and released from the pancreas and then transported to the small intestine, where it is cleaved into its active form (trypsin). Once digestion is complete, the enzyme is broken down and removed from the body. Mutations in the PRSS1 gene lead to a buildup of trypsin in the pancreas, stimulating inflammatory effects that lead to HP. HP progresses to chronic pancreatitis, and the prolonged inflammation induces damage to the pancreas, driving tumorigenesis (Canto, 2026; National Human Genome Research Institute, 2026; Schwarzenberg, 2025).
Figure 1
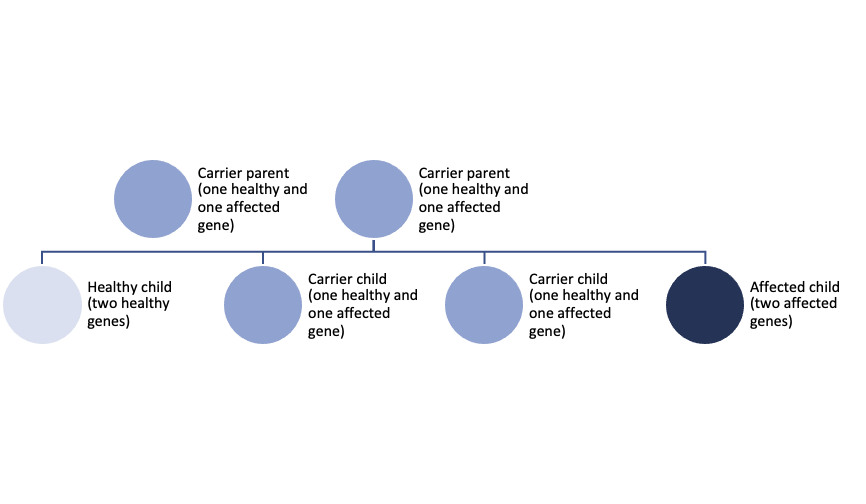
Autosomal Dominant (AD; Top) Versus Autosomal Recessive (AR; Bottom) Disease Inheritance
Hereditary Breast Cancer (BRCA1/2 Gene Mutations)
While mutations in BRCA1 and BRCA2 (BRCA1/2) genes are most commonly associated with an increased risk for breast and ovarian cancer, they are also among the most common inherited causes of pancreatic cancer. Females with BRCA1/2 mutations have an increased risk for breast, ovarian, melanoma, and pancreatic cancer, whereas males with BRCA1/2 mutations have an increased risk for breast, prostate, melanoma, and pancreatic cancer. Everyone is born with BRCA1 and BRCA2 genes. In their nonmutated state, BRCA1/2 genes function as essential tumor suppressor genes that promote the healthy growth, development, and division of specific cells in the body. Mutations in these genes disrupt their normal functions, increasing the propensity toward cancer development. Mutations in the BRCA1/2 genes follow an AD inheritance pattern (refer to Figure 1, top). In addition, mutations in the BRCA1/2 genes are the most common hereditary cause of familial pancreatic cancer, linked to a 2- to 6-fold higher risk of pancreatic cancer, a younger age of onset, and a more aggressive clinical course. Of the two gene mutations, the link with BRCA2 is better established. It carries a higher risk for developing pancreatic cancer, found in 5% to 10% of cases, whereas BRCA1 is identified in about 1% to 2% of cases. Mutations in BRCA1/2 are about ten times more common in those of Ashkenazi Jewish descent than in the general US population. Among Ashkenazi Jewish individuals with pancreatic cancer, BRCA2 mutations are found in up to 13.7% of cases (Cabebe, 2026a; Canto, 2026; Centers for Disease Control and Prevention [CDC], 2025; National Comprehensive Cancer Network [NCCN], 2026a, 2026b).
Peutz-Jeghers Syndrome
Peutz-Jeghers syndrome (PJS) is a rare disorder that affects an estimated 1 in 50,000 to 1 in 200,000 people. It is caused by a mutation in the STK11 gene (also called LKB1), which provides instructions for generating an enzyme called serine/threonine kinase 11, which functions as a tumor suppressor, regulating cellular growth and division. PJS is inherited in an AD pattern, with STK11 mutations detected in 50% to 80% of families with PJS. The remainder occur as a new (de novo) mutation in affected individuals. It typically presents during childhood and is characterized by benign growths (polyps) in the digestive tract called “hamartomatous polyps.” Although these are noncancerous polyps, they can cause bleeding and problems with the bowel, including intestinal obstruction. Classic signs of PJS in children and young adults include freckles and pigmented spots on the skin and in the mouth, called mucocutaneous hyperpigmentation. However, these typically fade during puberty, and the condition often goes undiagnosed. PJS increases the risk of developing several types of cancers, such as breast, colorectal (CRC), gastric, ovarian, testicular, lung, and many others. Without appropriate surveillance, these patients’ lifetime risk of developing cancer ranges from 85% to 95%. Regarding pancreatic cancer, the lifetime risk can range from 11% to 35% (ACS, 2025d, 2025e; Canto, 2026; Chung & Rodgers-Fouche, 2026; Sherman et al., 2025; To, 2024).
Hereditary Nonpolyposis Colorectal Cancer
Hereditary nonpolyposis colorectal cancer (HNPCC) or Lynch syndrome (LS) is most commonly known for its high-risk association with CRC; however, it is also associated with an increased risk of various other types of cancers, including uterine (endometrial), ovarian, gastric, pancreatic, urothelial, glioblastoma, biliary tract, and small intestine. Individuals inherit LS in an AD pattern (Figure 1, top). In the United States, it is estimated that 1 in 279 individuals (1.2 million people) have a gene mutation associated with LS; however, most are undiagnosed since identification depends on a cancer diagnosis. Changes in the protein expression of MLH1, MSH2, MSH6, or PMS2 genes are most commonly found in LS. Under physiologic conditions, these genes repair potential errors during DNA replication (the process during which DNA is copied in preparation for cell division); collectively, they are known as mismatch repair (MMR) genes. Since mutations in any of these genes impede the cell’s ability to repair DNA replication errors, abnormal cells continue to divide. Over time, the accumulated DNA replication errors can lead to uncontrolled cell growth and an increased propensity for cancer development. Mutations in the MLH1 or MSH2 gene are associated with a higher risk of developing cancer than mutations in the MSH6 or PMS2 genes, which carry a lower risk. Although gene mutations predispose individuals to cancer, not all people with these mutations will develop cancerous tumors. LS is responsible for 2% to 3% of CRCs and has a 70% to 80% lifetime risk of developing CRC. Greater than 90% of LS-related cancers are mismatch repair deficient (dMMR) or microsatellite instability-high (MSI-H), meaning they lack expression of at least one of the MMR proteins. According to the NCCN guidelines, patients with MSI-H or dMMR should be referred to a genetic counselor for formalized genetic testing. LS can only be confirmed by a specialized gene panel blood test (ACS, 2024c; Canto, 2026; CDC, 2026; Hall & Neumann, 2025; NCCN, 2026a; Villano, 2025a).
Ataxia-Telangiectasia Mutation
Advancements in technology have recently led to the discovery of new pancreatic cancer susceptibility genes, such as the ataxia-telangiectasia mutation (ATM) gene. The ATM gene provides instructions for generating serine/threonine kinase, an integral component of DNA repair. The ATM gene also plays an essential role in controlling the rate at which cells grow and divide and is necessary for the health and development of the nervous and immune systems. Ataxia-telangiectasia is a risk factor for pancreatic cancer as it is an immunodeficiency disease caused by mutations in the ataxia-telangiectasia gene. Ataxia-telangiectasia is an AR disease (Figure 1, bottom) of childhood that causes the immune system to break down, heightening susceptibility to illness. In AR disease, one abnormal gene is inherited from each parent, as the patient requires two copies of the mutation to be affected by the disease. A carrier has one abnormal gene (recessive) and one normal gene (dominant) and is clinically unaffected by the disorder. As demonstrated in Figure 1, two carriers have a 25% chance of having an unaffected child with two normal genes, a 50% chance of having an unaffected carrier, and a 25% chance of having an affected child. AR disorders are not typically seen in every generation of an affected family. Ataxia-telangiectasia is rare, occurring in only 1 out of 40,000 to 100,000 people worldwide. The condition confers increased cancer risk, most notably pancreatic and breast cancers. An association between ATM gene mutations and pancreatic cancer is evident, although the exact risks are not yet defined; additional research is needed to clarify this relationship (ACS, 2024a; Canto, 2026; Opal, 2026).
Familial Atypical Multiple Mole Melanoma
Familial atypical multiple mole melanoma (FAMMM) is a rare AD disorder most commonly caused by an inherited mutation in the p16/CDKN2A gene associated with skin and eye melanomas. FAMMM is characterized by numerous (usually more than 50) melanocytic nevi (moles) of different shapes and sizes and a family history of malignant melanoma. The family history typically includes one or more first- or second-degree relatives with melanoma (Genetic and Rare Diseases Information Center, 2026). FAMMM increases the risk of pancreatic cancer 20 to 47 times relative to the general population, and the prognosis is very poor (Canto, 2026; NCCN, 2026a, 2026b; Pancreatic Cancer Action Network, n.d.-d).
Familial Adenomatous Polyposis
Familial adenomatous polyposis (FAP) is known for the early onset of multiple gastrointestinal (GI) adenomas. Individuals with FAP tend to develop numerous benign polyps in their colon as early as their 20s and 30s. The number of polyps increases to thousands with advancing age, and unless the colon is removed, these polyps will develop into CRC. The condition is most commonly linked to pathogenic mutations in the adenomatous polyposis coli (APC) gene, inherited in an AD pattern and affecting the cell’s ability to maintain healthy growth and function. Aside from the risk of CRC, individuals with mutations in the APC gene have a fivefold greater likelihood of developing pancreatic cancer than the general population (ACS, 2025c; Canto, 2026; MedlinePlus, 2025).
PALB2 Gene Mutations
PALB2 is an inherited mutation of the PALB2 gene, which normally acts as a tumor suppressor by working with BRCA2 to repair damaged DNA. Mutations in the PALB2 gene may be inherited from either parent as it follows an AD inheritance pattern. PALB2 mutations are most notably associated with an increased risk for breast cancer but also carry an increased risk for pancreatic cancer; the exact risk is unknown. Mutations in the PALB2 gene have been identified in approximately 3% to 4% of familial pancreatic cancer cases (Canto, 2026; NCCN, 2026b; Pancreatic Cancer Action Network, n.d.-d; Peshkin & Isaacs, 2026).
Genetic Testing
The NCCN endorses the following criteria regarding the role of germline (genetic) testing in patients with pancreatic cancer: Germline testing is recommended for any patient with confirmed pancreatic cancer and those considering the molecular analysis of tumors for patients with metastatic disease using comprehensive gene panels for hereditary cancer syndromes. Referral to a genetic counselor is recommended for patients who test positive for a pathogenic mutation or patients with a positive family history of cancer, especially pancreatic cancer, regardless of mutation status. Regarding somatic testing, the NCCN endorses tumor/somatic profiling (testing on tumor tissue) for patients with locally advanced/metastatic disease who are candidates for anticancer therapy. Specifically, the guidelines recommend testing for, but not limited to, BRCA1/2, KRAS, PALB2, and MMR deficiency. DNA sequencing techniques can identify both germline and somatic mutations. Germline testing is required to determine if the mutation is inherited; these mutations can be identified by utilizing a saliva sample containing buccal cells or a peripheral blood sample. Genetic testing on the tumor specimen can identify genetic changes directly within the cancerous cells. This information helps identify treatment options likely to be the most effective (Cabebe, 2026c; Cardin & Singh, 2026; Mahon, 2020; NCCN, 2026a, 2026b).
Pancreatic Cancer Screening
Routine screening for pancreatic cancer is not recommended for the general population with average risk because the lifetime risk is low. However, many prospective studies have found that screening asymptomatic, high-risk individuals (those with a family history of at least two affected first-degree relatives or those with genetic syndromes that increase the risk) for pancreatic cancer was associated with earlier diagnosis, more curative surgical resections, and increased survival. Although several studies demonstrate the clinical benefit of screening high-risk individuals, universal guidelines regarding the age to start screening, the most effective screening modality, and the testing frequency are inconsistent. The decision to perform screening should start with a discussion of the risks and benefits with the patient. Patients who are not candidates for pancreas surgery should not undergo screening tests (Canto, 2026; NCCN, 2026a).
According to the NCCN guidelines, individuals suspected of having familial pancreatic syndrome or a high-risk genetic mutation should be referred to a genetic counselor. Individuals with a strong family history or specific known high-risk mutations (e.g., p16/CDKN2A) may opt to undergo heightened surveillance. The most commonly performed pancreatic cancer screening modalities include computerized tomography (CT), magnetic resonance imaging (MRI)/magnetic resonance cholangiopancreatography, or endoscopic ultrasound (EUS). Test selection depends on patient risk factors, patient preference, and availability of the testing modalities. All screening tests have limitations and potential harms, including false-positive and false-negative results. There is a high incidence of pancreatic abnormalities detected on screening tests (e.g., pancreatic cysts), and there are no clear evidence-based guidelines for properly surveying these lesions. Positive (abnormal) or inconclusive results often subject patients to invasive procedures (e.g., biopsy), which are not without risks, such as bleeding and infection. Additionally, medical imaging is subject to error, and screening tests are often imperfect and costly (Canto, 2026; NCCN, 2026a).
The NCCN and the International Cancer of the Pancreas Screening (CAPS) Consortium collectively endorse that the decision to undergo screening in high-risk patients should be individual. Clinicians are encouraged to discuss the pros and cons of screening, including an in-depth discussion about the potential limitations of screening and the lack of data regarding screening benefits. These discussions allow patients to ask questions and decide if screening is right for them. For individuals who opt to undergo screening, imaging should be performed in experienced, high-volume academic medical centers (Goggins et al., 2020; NCCN, 2026a, 2026b).
The CAPS Consortium has provided some guidance on pancreatic screening for high-risk individuals. They recommend screening the following high-risk groups:
- patient with PJS
- all carriers of the CDKN2A germline mutation
- carriers of BRCA1/BRCA2, ATM, PALB2, MLH1, MSH2, and MSH6 germline mutations with at least one first-degree relative with pancreatic cancer
- individuals with a familial pancreatic cancer kindred (i.e., one first-degree relative with pancreatic cancer who also has a first-degree relative with pancreatic cancer; Goggins et al., 2020)
The CAPS Consortium also provides some recommendations on the timing of surveillance based on family history and gene mutation. Surveillance should start at 40 for individuals with PJS or CDKN2A mutation. For individuals with familial pancreatic cancer kindreds, surveillance should begin at 50 to 55 or 10 years younger than the youngest affected relative. Surveillance starting at 45 to 50 or 10 years younger than the youngest affected relative is recommended for BRCA1, BRCA2, ATM, PALB2, MLH1, and MSH2. Screening should occur every 12 months for patients with no abnormalities and every 3 to 6 months for those with suspicious abnormalities (Goggins et al., 2020). The age at which screening should stop should be individualized based on the patient’s health status, life expectancy, and personal preference (Canto, 2026).
Pathophysiology
The pancreas is an organ of the digestive system that measures approximately 20 cm long and is positioned in the back of the abdomen, directly behind the stomach. As displayed in Figure 2, the pancreas is divided into three sections: the head, body, and tail. The head is the widest portion of the pancreas, located on the abdomen’s far-right side in the duodenal curve (the beginning of the small intestine). The body is the central portion of the pancreas and is situated behind the duodenum. The tail is the narrow left side of the pancreas that extends slightly upward and ends near the spleen (Norris, 2024; Rogers, 2022; Talathi et al., 2025).
Figure 2
Pancreas Anatomy
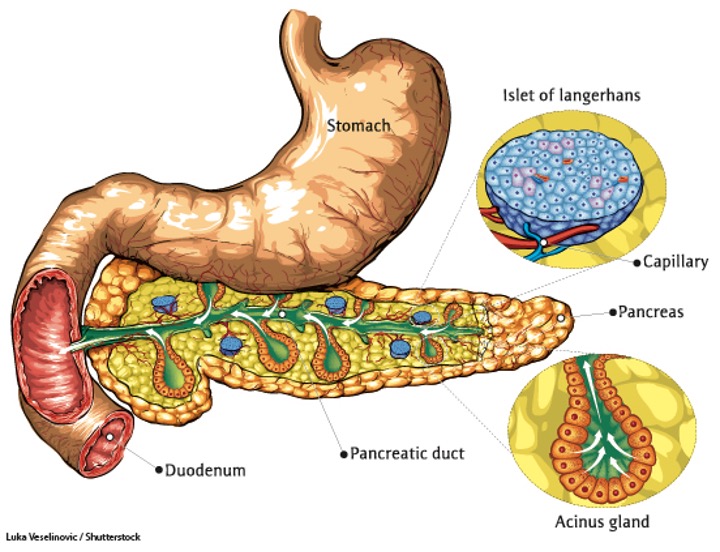
The pancreatic duct joins the biliary duct (from the liver) and extends the length of the pancreas. Blood is supplied to the pancreas by branches of the celiac and superior mesenteric arteries. The pancreas head drains venous blood through the portal vein and the superior mesenteric vein, and the body and tail drain via the splenic vein. The pancreas is unique in that it has both digestive (exocrine) and hormonal (endocrine) functions, serving essential metabolic roles as part of the digestive and endocrine systems (Norris, 2024; Rogers, 2022; Talathi et al., 2025).
Exocrine Pancreas
Most of the pancreas comprises exocrine cells, which contain two major types of epithelium (acinar and ductal), which cluster to form exocrine glands. Exocrine glands secrete enzymes into a network of ducts that release alkaline (bicarbonate-rich) fluids and other pancreatic enzymes to facilitate digestion. The acinar cells secrete the enzymes, and the ductal cells secrete the bicarbonate fluid. The acinar cells are organized into spherical lobule-like structures surrounding secretory ducts. The secretions are called proenzymes at this point since they remain inactivated. They drain into a duct system that leads to the pancreatic duct before emptying into the common bile duct and being transported to the duodenum. Once the proenzymes enter the duodenum, they become activated by enterokinase, an enzyme secreted by the duodenal mucosa. Once activated, the pancreatic enzymes help break down carbohydrates, fats, proteins, and acids. Secretin is a substance that stimulates the acinar cells to release a bicarbonate-rich fluid to neutralize the stomach acids (chyme), which pass from the stomach into the duodenum. The pancreatic enzyme amylase digests carbohydrates, and lipase digests triglycerides, cholesterol, and lipids. Amylase and lipase are used as markers of pancreatic inflammation (i.e., pancreatitis). Amylase may be measured in the urine or blood, whereas lipase is only measured in the blood. An expected serum amylase level is 25 to 125 U/L, and an expected serum lipase level is 10 to 140 U/L (American Board of Internal Medicine [ABIM], 2026; Norris, 2024; Rogers, 2022; Talathi et al., 2025).
Endocrine Pancreas
The endocrine glands account for a much smaller percentage of the pancreas. The endocrine glands primarily consist of the islets of Langerhans, which produce and secrete hormones (glucagon and insulin) into the bloodstream. These hormones regulate a significant portion of the carbohydrate metabolism within the body by facilitating the formation and cellular uptake of glucose (Norris, 2024; Rogers, 2022; Talathi et al., 2025). The three types of hormone-secreting cells that comprise the islets of Langerhans include the following:
- alpha (α)-cells (secrete glucagon and comprise 15% to 20% of islet cells)
- beta (ß)-cells (secrete insulin and comprise 65% to 80% of islet cells)
- delta (D)-cells (secrete somatostatin and gastrin and comprise 3% to 10% of islet cells; Norris, 2024; Rogers, 2022; Talathi et al., 2025)
A major disorder of the endocrine pancreas is diabetes mellitus (DM), a chronic disease impacting multiple body systems due to abnormal insulin production, impaired insulin utilization, or both. Type 1 diabetes mellitus (T1DM) is characterized by the autoimmune destruction of the pancreatic ß-cells, leading to the total absence of insulin production. A genetic predisposition is typically compounded by exposure to a virus that contributes to this autoimmune condition. Autoantibodies to the islet cells cause a decrease in normal function before other symptoms of T1DM appear. Patients with T1DM depend on external insulin for survival since the hormone is not produced internally. In type 2 DM (T2DM), insulin is either generated in insufficient quantities or used poorly by the tissues, or both. The most common risk factor for T2DM is elevated BMI (30 or greater), especially abdominal adiposity. Those with T2DM are insulin-resistant and are managed with oral hypoglycemics (e.g., metformin [Glucophage]). If control of hyperglycemia is not achieved, patients with T2DM may eventually require external insulin (Hinkle et al., 2025; Norris, 2024; Rogers, 2022; Talathi et al., 2025).
Normal insulin metabolism occurs through the continuous insulin release by the ß-cells in the islets of Langerhans of the pancreas. Insulin synthesis begins with its precursor, proinsulin. Enzymes break down proinsulin to produce insulin and C-peptide in equal amounts. This byproduct, C-peptide, is useful when assessing pancreatic ß-cell function as it can be measured in the urine and blood. The average amount of insulin secreted daily by a healthy adult is 40 to 50 units or 0.6 units/kg of body weight. Insulin acts as an anabolic or storage hormone in the body. The insulin secreted with food intake promotes glucose transport into the cells for energy by unlocking receptor sites in the skeletal muscle and adipose tissue. Skeletal muscles and fatty tissue are considered insulin-dependent; the brain, liver, and blood cells do not depend on insulin and only require an adequate glucose supply for normal functioning. While liver cells (hepatocytes) are not insulin-dependent, they have insulin receptor sites facilitating hepatic glucose uptake and its conversion to glycogen (Hinkle et al., 2025; Norris, 2024; Rogers, 2022; Talathi et al., 2025).
As blood glucose increases after a meal or food intake, glucose is stored as glycogen in the liver and muscle tissue. Concurrently, insulin secretion inhibits gluconeogenesis (glucose production from nonsugar substances), enhances fatty tissue deposition, and increases protein synthesis. The reduced insulin that occurs overnight (or from fasting) causes the liver to release glucose, the muscles to release proteins, and the fatty tissue to release fat. Counterregulatory hormones such as glucagon, epinephrine, growth hormone, and cortisol oppose the effects of insulin. They increase blood glucose by stimulating the production of glucose and liver output and decreasing glucose movement into the cells. Insulin secretion is designed to maintain a stable blood glucose level of 70 to 120 mg/dL. A healthy blood glucose level is typically maintained by regulating the release of glucose for energy during fasting, food intake, and the production and release of insulin and the counterregulatory hormones. Less is understood about the function of pancreatic somatostatin and gastrin. Somatostatin is an essential hormone in carbohydrate, fat, and protein metabolism. It suppresses the release of other hormones generated in the pancreas and functions to maintain the homeostasis of nutrients. Gastrin helps to control the secretion of glucagon. All hormonal pancreatic secretions pass through the portal vein into the liver (Hinkle et al., 2025; Norris, 2024; Rogers, 2022; Talathi et al., 2025).
For a detailed account of diabetes, refer to the Diabetes NursingCE courses on our site.
Pancreatic Cancer Subtypes
Pancreatic tumors develop in the endocrine and exocrine glands and are grouped accordingly (Suriawinata, 2025).
Exocrine Tumors
Exocrine tumors account for at least 90% of all pancreatic cancer diagnoses, with ductal adenocarcinoma comprising the vast majority. Exocrine tumors are outlined in Table 2 (Suriawinata, 2025).
Table 2
Exocrine Tumors
Subtype | Description |
Ductal adenocarcinoma |
|
Adenosquamous |
|
Acinar cell carcinoma |
|
Giant cell carcinoma |
|
(NCCN, 2026b; Pancreatic Cancer Action Network, n.d.-e; Suriawinata, 2025)
Precursor Lesions to Ductal Adenocarcinoma
There are three well-cited noninvasive precursor lesions to ductal adenocarcinoma: pancreatic intraepithelial neoplasia (PanIN), mucinous cystic neoplasm (MCN), and intraductal papillary mucinous neoplasms (IPMN). These tumors are usually small, cystic, and discovered incidentally. They are often benign when diagnosed but have a chance of becoming cancerous. The incidence increases with age, but most commonly occurs in those aged 60 to 70. Many are managed conservatively with heightened surveillance (e.g., annual radiographic monitoring) and never progress to invasive cancer. Tumors with certain high-risk features, such as IPMNs arising from the main pancreatic duct, require surgical resection and monitoring for recurrence (NCCN, 2026b; Pancreatic Cancer Action Network, n.d.-e; Suriawinata, 2025).
Endocrine Tumors
Endocrine tumors are rare; they account for less than 5% of all pancreatic tumors, with only 1,000 new cases in the United States annually. These islet cell tumors (or pancreatic neuroendocrine tumors [PNETs]) denote cancer of the hormone-producing cells. PNETs may be functioning (meaning they generate hormones) or nonfunctioning (do not generate hormones). Most PNETs are functional (75%) and typically present with symptoms of hormone hypersecretion. PNETs are characteristically small, well-circumscribed tumors that are difficult to distinguish from healthy islet cells. They are not always malignant and may or may not produce symptoms. The presence of metastases is the most reliable criterion for establishing a malignant process. Table 3 outlines the three most common functional PNETs (National Cancer Institute [NCI], 2025b; Norris, 2024; Strosberg, 2026).
Table 3
Functional Pancreatic Neuroendocrine Tumors (PNETs)
Type | Description |
Gastrinoma |
|
Insulinoma |
|
Glucagonoma |
|
(NCI, 2025b; Norris, 2024; Strosberg, 2026)
Clinical Manifestations
The signs and symptoms of pancreatic cancer typically occur late in the illness, are vague and nonspecific, and often mimic other conditions. Patients can experience bloating, anorexia, fatigue, mid-epigastric or back pain, and weight loss. It is typical for an individual with pancreatic cancer to ignore initial symptoms for several months until jaundice (yellowing of the skin and eyes caused by a buildup of bilirubin) or other prominent signs are present. Ominous signs usually develop late and only after invasion or obstruction of nearby tissue. Pancreatic cancer can also cause diabetes in 25% to 50% of patients, leading to glucose intolerance (i.e., polydipsia and polyuria). Furthermore, manifestations of the disease can differ based on the tumor’s anatomical location (ACS, 2024e; Fernandez-del Castillo & Singh, 2026; Norris, 2024; Puckett & Garfield, 2024; Villano, 2025b).
Head of the Pancreas
When the tumor involves the pancreatic head, symptoms typically appear earlier than those involving the body or tail. Pancreatic head tumors tend to occlude the distal common bile duct, causing duct obstruction and inducing a constellation of symptoms, including jaundice, weight loss, and pain. Jaundice with pain is much more common than painless jaundice and is the most common presenting symptom, prompting patients with pancreatic head tumors to seek medical care. Interestingly, patients with pancreatic head tumors have a high incidence of depression and anxiety, which has been shown to predate the diagnosis by as many as 3.5 years. This psychological phenomenon was first identified in 1931. Although the relationship is poorly understood, research has demonstrated a 2 to 3 times higher incidence of depression in patients with pancreatic cancer than in other intra-abdominal cancers. The proposed rationale is that hormonal neuroendocrine substances circulate through the central nervous system. Other symptoms of pancreatic head tumors include diarrhea, indigestion, weakness, and anorexia (ACS, 2024e; Fernandez-del Castillo & Singh, 2026; Norris, 2024; Puckett & Garfield, 2024; Villano, 2025b; Yaskin, 1931).
Body of the Pancreas
Tumors in the pancreatic body produce signs and symptoms late in the illness, making it nearly impossible to detect early. The predominant presenting symptom of pancreatic body tumors is severe epigastric pain, intensifying about 3 to 4 hr after meals. The tumor compresses or displaces the stomach, inducing intense pain when the stomach is full; this pain is often accompanied by vomiting. The pain may be relieved by sitting up, leaning forward, or lying in the fetal position to alleviate the pressure on the stomach. In many cases, the tumor is palpable on abdominal examination and may be accompanied by splenomegaly (enlarged spleen) caused by tumor compression of the splenic vein. Tumors in the pancreatic body and tail do not induce jaundice but cause more pain and weight loss than those in the pancreatic head (ACS, 2024e; Fernandez-del Castillo & Singh, 2026; Norris, 2024; Puckett & Garfield, 2024; Villano, 2025b).
Tail of the Pancreas
In addition to the characteristics described above, tumors in the pancreatic tail are known for their silent growth and insidious progression, typically diagnosed in advanced stages. The most common symptoms include left upper quadrant pain, generalized weakness, anorexia, and indigestion. In addition to splenomegaly, signs of portal hypertension and ascites may be present from thrombosis of the portal system or liver damage. Upper GI bleeding (GIB) may also present with advanced pancreatic tail tumors. Weight loss is often accompanied by cachexia and muscle wasting (ACS, 2024e; Fernandez-del Castillo & Singh, 2026; Norris, 2024; Puckett & Garfield, 2024; Villano, 2025b). Ominous physical examination findings suggesting metastatic pancreatic cancer include the following:
- left supraclavicular adenopathy (Virchow node)
- periumbilical adenopathy (Sister Mary Joseph nodes)
- deep metastases in the pelvis encircling the perirectal region (Blumer’s shelf; ACS, 2024e; Fernandez-del Castillo & Singh, 2026; Norris, 2024; Puckett & Garfield, 2024; Villano, 2025b)
PNETs
As noted earlier, PNETs do not always cause symptoms. Functional PNETs secrete excess hormones, which can induce various unusual manifestations and diverse signs and symptoms (Refer to Table 3; NCI, 2025b; Norris, 2024; Strosberg, 2026).
Diagnostic Workup
Pancreatic cancer remains one of the most challenging cancers to diagnose based on its anatomical location and subtle onset. When pancreatic cancer is suspected, an abdominal ultrasound (US) is the most common initial diagnostic test, especially for tumors in the pancreatic head. US is a safe, noninvasive imaging modality that uses sound waves to generate images of internal body structures. Also called sonography, US does not use x-rays or ionizing radiation. Images are obtained by placing a small probe (transducer) and ultrasound gel on the skin. The transducer produces sound waves at very high frequencies, which exceed the threshold of human hearing. The sound waves capture images of the internal organs and blood flow through vessels. Some transducers are placed directly inside the body to optimize image quality, such as through the GI tract or vagina. Abnormalities detected on US typically require follow-up imaging with a CT scan of the abdomen, which is superior in evaluating the abdominal structures, identifying suspicious features of the mass, and detecting intestinal obstruction, liver metastases, and nearby lymphadenopathy (enlarged lymph nodes). Although several studies are available to assist with diagnosing pancreatic cancer, the only way to confirm the diagnosis and establish the specific clinical features of the tumor is through a biopsy specimen. Most pancreatic biopsies are obtained using nonsurgical procedures; the two most common techniques include EUS and endoscopic retrograde cholangiopancreatography (ERCP; Fernandez-del Castillo & Singh, 2026; NCCN, 2026b; RadiologyInfo.org, 2024a, 2024b).
EUS
EUS is a specialized imaging technique that generates detailed, high-resolution, three-dimensional images of the pancreas and surrounding structures. It also facilitates the tissue sampling of the suspicious mass. EUS is performed to confirm the primary site of pancreatic cancer involvement and to obtain a tissue biopsy. The patient requires conscious sedation for this procedure. An endoscope (a thin, tube-like instrument with a light on the end) is guided down the esophagus and through the stomach until it reaches the duodenum. At the end of the tube, a US device emits sound waves to generate images of the pancreas, blood vessels, bile ducts, and nearby tissues. A needle biopsy (fine-needle aspiration [FNA] or core needle biopsy) is taken from the tumor site during the procedure. Studies have demonstrated that EUS-FNA is highly accurate in establishing a diagnosis of pancreatic cancer with an accuracy of 90% to 95%, a sensitivity of 89% to 92%, and a specificity of 96%. EUS is an outpatient procedure performed in a hospital or same-day surgery center using anesthesia. Although complications from an EUS are rare, some of the most commonly cited complications include infection, pancreatitis, GIB, tearing, and adverse reactions from anesthesia (Cabebe, 2026c; Fernandez-del Castillo & Singh, 2026; Gress, 2024; RadiologyInfo.org, 2024a, 2024b).
ERCP
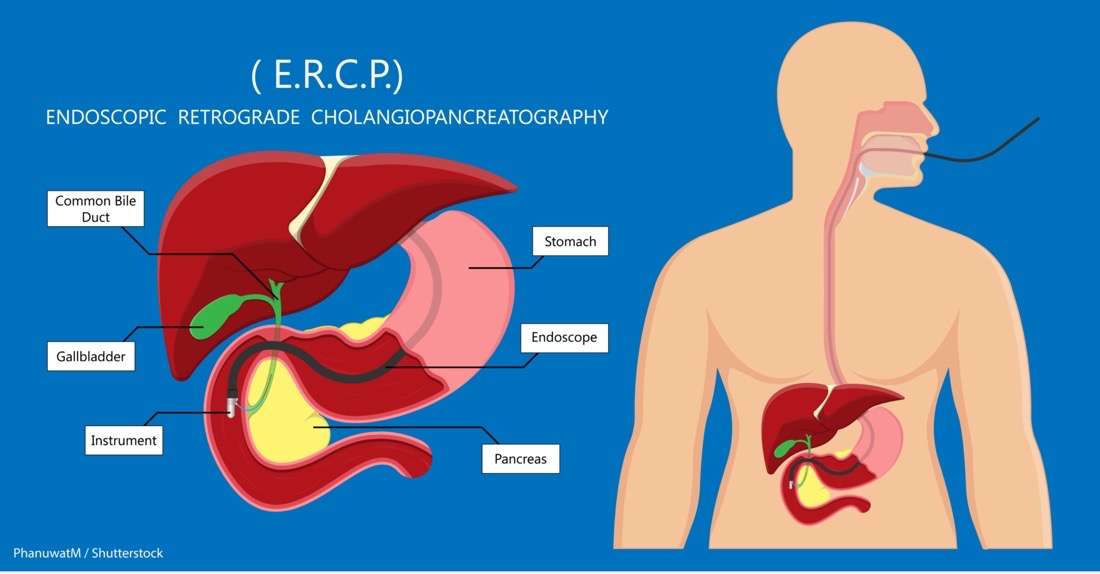
There are only a few differences between an EUS and an ERCP. A key difference is that the ERCP typically utilizes radiographic imaging and contrast. Most sources agree that an ERCP produces higher quality images and allows for enhanced visualization of the organs and ducts compared with a standard EUS. Figure 3 demonstrates that an endoscope is inserted through the esophagus into the duodenum during an ERCP. Air is inserted through the endoscope into the duodenum to make it easier to see the organs, and a catheter is inserted into the endoscope until it reaches the bile and pancreatic ducts. Next, contrast material is injected, and radiographs are taken to evaluate for gallstones, strictures, or blockages. Similar to an EUS, an FNA or core-needle biopsy can be taken. However, an ERCP additionally allows for more advanced therapeutics, such as sphincterotomy or stenting procedures, to manage identified problems. A sphincterotomy involves making a small incision to enlarge the bile duct or the opening of the pancreatic duct to improve drainage or alleviate any blockage. Stenting involves placing a small plastic tube within a blocked or narrowed duct to improve drainage. Some stents are designed to pass through the intestine after a few weeks, whereas others must be removed or changed every 3 to 4 months. Permanent stents are typically made of metal. ERCP is the gold standard for alleviating biliary drainage in patients with biliary obstruction of the distal common bile duct, a common complication of pancreatic cancer. The most common ERCP complications include pancreatitis and cholangitis (inflammation of the bile duct system; Cabebe, 2026c; Pancreatic Cancer Action Network, n.d.-b; RadiologyInfo.org, 2024b; Villano, 2025b).
Figure 3
Endoscopic Retrograde Cholangiopancreatography (ERCP)
Once pancreatic cancer is diagnosed, the NCCN (2026b) guidelines endorse the essential pancreatic cancer staging components outlined in Table 4.
Table 4
Components of Diagnostic Staging Workup
Complete history and physical |
Laboratory tests:
|
Dedicated imaging studies of the pancreas are as follows:
|
Imaging to evaluate for other sites of disease as follows:
|
(Cabebe, 2026c; Fernandez-del Castillo & Singh, 2026; NCCN, 2026b; Villano, 2025b)
CA 19-9
Tumor markers are substances, or proteins, secreted by cancer cells or by the body’s response to cancer’s presence. Healthy cells also generate tumor markers in smaller quantities, so that healthy people can have small amounts of tumor markers in their blood. Although tumor markers are nonspecific and not beneficial when used in isolation, they can help evaluate treatment response and cancer recurrence. Although no tumor marker is sufficiently sensitive or specific to be considered 100% reliable and accurate for screening pancreatic cancer, CA 19-9 is the most specific tumor marker. CA 19-9 is a sialylated oligosaccharide found on circulating mucins in patients with cancer. It is normally present in biliary tract cells. Elevated CA 19-9 levels can also occur in nonmalignant conditions such as gallstones, liver disease, cirrhosis, pancreatitis, obstruction, cholangitis, or cystic fibrosis. An expected CA 19-9 level is 0 to 37 U/mL. The NCCN guidelines recommend evaluating CA 19-9 as a baseline marker during the diagnostic workup and periodically to assess treatment response. A decline in the CA 19-9 level following systemic therapy typically denotes a therapeutic response to treatment. Although CA 19-9 is an established prognostic marker for pancreatic cancer, it remains unclear how CA 19-9 monitoring should guide multimodal treatment or what degree of decline constitutes a meaningful treatment response (ABIM, 2026; Cabebe, 2026c; Fernandez-del Castillo & Singh, 2026; NCCN, 2026b).
Pancreatic Cancer Staging
The cancer stage at diagnosis guides treatment options and strongly influences overall survival. The universal pancreatic cancer staging system is the American Joint Committee on Cancer’s (AJCC) Tumor, Node, Metastasis (TNM) System. As cited within the NCCN guidelines, the AJCC describes specific characteristics to assign stages I through IV, as outlined in Table 5 and demonstrated in Figure 4. Cancer staging reflects the cell type, tumor grade, anatomical location of the tumor, and extent of malignancy. Within the TNM staging system, T denotes the size of the tumor and if it has grown into nearby tissue, N refers to the presence of cancer in the lymph nodes, and M indicates if cancer has metastasized to other parts of the body beyond the origin site. The most common patterns of initial spread for pancreatic cancers include the liver, peritoneum, regional lymph nodes, and Virchow nodes (Amin et al., 2017; Fernandez-del Castillo & Singh, 2026; NCCN, 2026b; NCI, 2024).
Table 5
Pancreatic Cancer Staging
Stage | TNM | Description |
– | TX | Primary tumor cannot be assessed |
– | T0 | No evidence of primary tumor |
0 | Tis | Carcinoma in situ |
I | T1 | Tumor ≤2 cm in greatest dimension |
II | T2 | Tumor >2 cm and ≤4 cm in greatest dimension, but has not grown outside of the pancreas |
III | T3 | Tumor >4 cm in greatest dimension |
T4 | Tumor involves the celiac axis, superior mesenteric artery, and/or common hepatic artery, regardless of size | |
IV | Any T | The tumor has spread (metastasized) to distant sites or organs outside the pancreas (e.g., the liver) |
(Amin et al., 2017; Fernandez-del Castillo & Singh, 2026; NCCN, 2026b; NCI, 2024)
Figure 4
Pancreatic Cancer Staging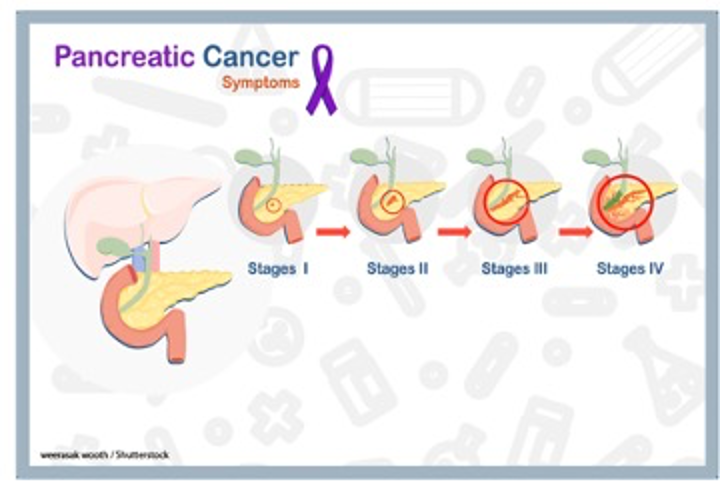
Tumor Grade
Tumor grade measures how different the cancer cells look compared to healthy cells under the microscope. It is based on cell differentiation and varies from low grade (grade 1) to high grade (grade 3). Grade 1 is well-differentiated and appears similar to healthy cells, whereas grade 3 is poorly differentiated (i.e., does not resemble healthy cells) and most aggressive (ACS, 2024d; NCCN, 2026b).
Treatment Modalities
Pancreatic cancer is difficult to treat due to its biological nature and advanced stage at diagnosis. Treatment for pancreatic cancer is usually multifactorial, involving combined modalities, and primarily depends on the cancer stage. The NCCN provides evidence-based treatment guidelines for pancreatic cancer according to histopathological findings, genetics, staging, and other specific features. The guidelines are widely utilized in cancer care and guide medical decision-making throughout the patient’s disease trajectory. Due to the aggressive biology of pancreatic cancer and the advanced stage of diagnosis for most patients, treatment is chronic, and most patients experience periods of remission and relapse. All patients need close monitoring and surveillance after treatment to monitor for recurrence, and many receive maintenance therapy. This section will review the most common treatment strategies (NCCN, 2026b; NCI, 2025a; Puckett & Garfield, 2024; Villano, 2025b).
Surgery
Surgery is the primary mode of treatment for resectable pancreatic cancer. The role of surgery in pancreatic cancer is limited to tumors confined to the pancreas without any evidence of spread to distant lymph nodes or other organs. The surgical technique varies based on the tumor’s location and relationship to surrounding blood vessels. The surgical goals are to optimize the quality of life, completely excise the tumor, obtain long-term cancer control, and reduce morbidity. Surgical resection offers the only chance of cure for exocrine pancreatic cancer; however, only 15% to 20% are resectable, often due to vascular invasion. Even with complete resection, high recurrence rates are likely and lead to poor prognosis. Chemotherapy, radiation, or combined options are often used to help improve outcomes. The risks and side effects of surgery depend on the size and degree of cancer invasion, the extent of surgery, and the structures removed. All surgeries and invasive procedures are accompanied by risks, such as adverse reactions to anesthesia, bleeding, blood clots, fistula formation (an abnormal connection between two hollow spaces within the body), bowel and bladder injury, infection, and life-threatening sepsis (Cabebe, 2026b; Fernandez-del Castillo & Jimenez, 2026b; Mamon et al., 2026b; NCCN, 2026b).
Pancreatoduodenectomy (Whipple Procedure)
A Whipple procedure is one of the most common surgeries to manage pancreatic tumors confined to the pancreatic head. However, this type of surgery is also indicated for pancreatic ductal tumors, cholangiocarcinoma (bile duct cancer), and duodenal masses. It is a complex surgery in which the head of the pancreas, gallbladder, duodenum, a portion of the stomach, and surrounding lymph nodes are removed, and the remaining part of the pancreas and digestive organs are reconnected. Alternatively, some patients may undergo a pylorus-preserving Whipple, a modified version of the procedure in which the entire stomach and the stomach valve (pylorus) are kept in place. Patients usually require hospitalization for at least a week following a Whipple to allow for close monitoring as the body adapts to the significant changes. The mortality rate associated with a Whipple procedure is 6.6%. The most common postoperative complication is delayed gastric emptying (gastroparesis), a motility disorder in which the stomach does not empty food as quickly as possible. Gastroparesis induces nausea, vomiting, bloating, abdominal cramping, and anorexia, and symptoms typically improve within 7 to 10 days. If gastroparesis continues, patients may require nutrition support through a feeding tube or total parenteral nutrition intravenously. The most serious complication is an abdominal infection caused by a pancreatic leak (leakage in the area that the pancreas connects to the intestine) or fistula. These complications occur in about 10% of cases and require timely antibiotic administration to minimize morbidity and mortality. Long-term GI effects are common; many experience ongoing diarrhea, flatus, and stomach cramping, requiring dietary adjustments. Most patients require the long-term and potentially permanent use of exogenous pancreatic enzymes to facilitate proper digestion after a Whipple (Cabebe, 2026b; Fernandez-del Castillo & Jimenez, 2026b; Reber, 2025).
Distal Pancreatectomy with En-bloc Splenectomy
In rare cases, pancreatic body or tail tumors are detected early enough to be considered curable, usually as an incidental finding in patients undergoing workup for an unrelated issue. In these patients, distal pancreatectomy with splenectomy has historically been the most common procedure in which the pancreas and spleen are removed. The spleen serves vital immunologic and hematologic functions, such as filtering the blood of debris. Excising the spleen increases the risk of infection, hypercoagulability, diabetes, and other hematological complications. Therefore, in recent years, many surgeons have advocated for spleen-preserving distal pancreatectomy, which carries a lower incidence of postoperative complications. A distal pancreatectomy is associated with a 0.8% to 5% mortality rate and carries the risk of pancreatic stump leak, hemorrhage, and endocrine insufficiency (Cabebe, 2026b; Hines, 2024; NCCN, 2026b).
Radiation Therapy
Radiation therapy is a localized treatment that delivers a precisely measured amount of high-energy, highly focused rays of ionizing radiation to the tumor while providing as little injury as possible to surrounding tissue. Radiation causes cellular damage to cancer cells, leading to biological changes in the DNA, rendering cells incapable of reproducing or spreading. All healthy and cancer cells are vulnerable to the effects of radiation and may be injured or destroyed; however, healthy cells can repair themselves and remain functional. The total radiation dose is hyperfractionated, which means it is delivered to the tumor in small, divided doses or fractions rather than all at once. Hyperfractionation allows healthy cells a chance to recover between treatments. The total number of fractions (doses) administered depends on the tumor size, location, reason for treatment, patient’s overall health, performance status, goals of therapy, as well as consideration of any other concurrent therapies the patient is receiving (ACS, 2025f; Mamon et al., 2026b; Nettina & Nelson-Tuttle, 2024; Pancreatic Cancer Action Network, n.d.-f).
External Radiation
External beam radiation therapy (EBRT) delivers radiation from a source outside the body and is the most common type of radiation therapy used for pancreatic cancer. Traditionally, radiation beams could only match the tumor’s height and width, exposing more healthy tissue to the consequences of radiation. Over recent decades, 3D conformational radiation therapy (3D-CRT) has become the mainstay of EBRT for many solid tumors, including pancreatic cancer. 3D-CRT is credited with the ability to reshape the radiation beam to match the tumor’s shape. Further advancements in imaging technology have led to more precise treatment mechanisms that allow even more radiation to reach the tumor. Intensity-modulated radiation therapy (IMRT) is a newer, highly conformal form of radiation that further reduces unintended exposure to healthy tissues. While 3D-CRT and IMRT are very similar in that they both target the tumor while sparing healthy tissue, IMRT allows modulation of the radiation beam’s intensity, delivering a higher radiation dose to a precise location. The enhanced targeting technology of IMRT allows higher radiation doses to reach the disease site, enhancing clinical outcomes and limiting side effects. Stereotactic body radiation therapy (SBRT) is a technique in which extremely high biological doses of radiation are administered over a few short treatments. The target area is affected to a higher degree over a shorter period with minimal impact on healthy tissue. In pancreatic cancer treatment, the role of SBRT continues to evolve as it has been shown to improve cancer-related pain and quality of life. It is attractive because it can be completed quickly, requiring less time away from chemotherapy. SBRT has a relatively favorable toxicity profile with minimal systemic effects and, therefore, is potentially beneficial for patients who are not candidates for systemic therapy, such as older adults, those with poor performance status, or multiple complex medical comorbidities (ACS, 2025f; Burkon et al., 2022; Mamon et al., 2026b; NCCN, 2026b; Pancreatic Cancer Action Network, n.d.-f).
Radiation Side Effects
Radiation side effects depend on the specific area(s) of the body exposed and the dose received. Superficial skin irritation at the site where the EBRT beams aim is common and can include redness, blistering, and sunburn. GI symptoms are common due to the tumor’s anatomical location and the impact of the radiation beams on surrounding tissues and structures. Common symptoms of GI toxicity may include nausea, vomiting, diarrhea, anorexia, bowel incontinence, abdominal pain, bloating, gastroparesis, heartburn, and esophagitis. Systemic effects may include fatigue, weakness, dehydration, scarring, fibrosis, and adhesion formation (the tissues impacted by radiation stick together; ACS, 2025f; Pancreatic Cancer Action Network, n.d.-f).
Systemic Therapy
According to the NCCN (2026b), systemic therapy is used in all stages of pancreatic cancer. Systemic therapy includes intravenous (IV) and oral chemotherapy, targeted therapy, and immunotherapy.
Chemotherapy
Chemotherapy, also called cytotoxic or antineoplastic therapy, encompasses a group of high-risk, hazardous drugs that are intended to destroy as many cancer cells with as minimal effect on healthy cells as possible. Chemotherapy generally works by interfering with the normal cell cycle, impairing DNA synthesis and cell replication, and preventing cancer cells from dividing, multiplying, and forming new cancer cells. Surgery for pancreatic cancer may or may not be preceded by neoadjuvant chemotherapy or followed by adjuvant therapy. Neoadjuvant chemotherapy is administered to shrink the tumor so that surgical intervention may not need to be as extensive. In pancreatic cancer, neoadjuvant chemotherapy may shrink the tumor enough so that the surgeon can perform a Whipple or other surgical resection of the tumor. Adjuvant therapy is given following surgery and aims to eradicate any micro-metastases and prevent cancer recurrence. Micro-metastases are a small collection of cancer cells too tiny to be identified on imaging scans that have detached from the original tumor and spread to other parts of the body. The danger with micro-metastases is that they can coalesce and form additional cancerous tumors within the body. Chemoradiation (concurrent chemotherapy and radiation therapy) is another common treatment typically administered after systemic chemotherapy. Chemotherapy acts as a radiosensitizer, thereby rendering cancer cells more vulnerable to the toxic effects of radiation. Palliative chemotherapy aims to relieve or delay cancer symptoms, enhance comfort, reduce symptom burden, and improve quality of life with reduced doses adjusted to minimize treatment-related toxicity (Cabebe, 2026b; Mamon et al., 2026a, 2026b; Nettina & Nelson-Tuttle, 2024; Pancreatic Cancer Action Network, n.d.-a).
A wide range of chemotherapeutic agents are used in pancreatic cancer, usually given in combinations of two or three drugs. The drug selection depends on the cancer stage, the treatment intent (curative or palliative), prior lines of therapy, and the patient’s clinical status (NCCN, 2026b). Table 6 provides a list of the preferred regimens. Some of the most common chemotherapy agents used for pancreatic cancer include the following:
- 5-fluorouracil (5-FU)
- calcium Leucovorin (Folinic acid)
- capecitabine (Xeloda)
- irinotecan (Camptosar)
- liposomal irinotecan (Onivyde)
- oxaliplatin (Eloxatin)
- gemcitabine (Gemzar)
- cisplatin (Platinol)
- albumin-bound paclitaxel (Abraxane; NCCN, 2026b; Mamon et al., 2026a, 2026b; Pancreatic Cancer Action Network, n.d.-a)
Table 6
Pancreatic Cancer Regimens
Regimen Name | Drugs Included |
FOLFIRINOX |
|
Modified FOLFIRINOX |
|
NALIRIFOX |
|
FOLFOX |
|
FOLFIRI |
|
FOLFOXIRI |
|
Capecitabine |
|
Concurrent chemoradiation |
|
Gem/Cis |
|
Gem/Abraxane |
|
PAXG |
|
(Mamon et al., 2026a, 2026b; NCCN, 2026b; Pancreatic Cancer Action Network, n.d.-a)
The FDA recently approved a wearable device called Optune Pax, which can be used in combination with a standard chemotherapy regimen (Gem/Abraxane) for adults with locally advanced pancreatic cancer. This device delivers a treatment called Tumor Treating Fields Therapy. Worn on the skin, the device uses alternating electric fields to disrupt cancer cell proliferation while minimizing damage to healthy tissue (FDA, 2026b; Mamon et al., 2026a; Pancreatic Cancer Action Network, n.d.-a).
Chemotherapy Side Effects
The side effects of chemotherapy vary based on the drug type, dosage, duration of treatment, and specific patient factors. As a group, the most common side effects include lowering of the blood counts (anemia, thrombocytopenia, neutropenia), fatigue, nausea, anorexia, alopecia (hair loss), mucositis (mouth sores), diarrhea, skin changes, and peripheral neuropathy (damage to the sensory nerves). Table 7 reviews some of each agent’s unique side effects and key considerations (ACS, 2025a; Pancreatic Cancer Action Network, n.d.-a).
Table 7
Pancreatic Cancer Chemotherapy Agents and Clinical Considerations
Chemotherapy | Clinical Considerations |
5-Fluorouracil (5-FU) |
|
Capecitabine (Xeloda) |
|
Oxaliplatin (Eloxatin) |
|
Irinotecan (Camptosar) |
|
Gemcitabine (Gemzar) |
|
Cisplatin (Platinol) |
|
(ACS, 2025a; Casale & Patel, 2024; ONS Voice, 2024, 2025; Pancreatic Cancer Action Network, n.d.-a; Reyhanoglu & Smith, 2023; US Food & Drug Administration [FDA], 2019, 2026c)
Bone Marrow Suppression. Bone marrow suppression refers to three main hematopoietic consequences of chemotherapy: neutropenia (reduction in white blood cells [WBCs]), anemia (reduction in red blood cells), and thrombocytopenia (reduction in platelets; Nettina & Nelson-Tuttle, 2024; Norris, 2024).
Neutropenia. When the body’s natural defense, the immune system, is suppressed due to chemotherapy, the patient is considered neutropenic; the ability to mount an immune response to everyday germs, bacteria, or pathogens is poor. As a result, the patient is highly susceptible to illness and is at heightened risk for life-threatening bloodstream infections (bacteremia or sepsis). Neutropenia is defined by an absolute neutrophil count of 1,500/mm3 or less and is the primary dose-limiting toxicity of chemotherapy. The most common sign of infection in a patient with neutropenia is a fever. Febrile neutropenia is a medical emergency requiring prompt evaluation, workup, and the initiation of empiric antibiotics. HCPs must counsel patients on strategies to avoid infection, such as thorough handwashing, hygiene, and avoiding others who are ill. Patients should also avoid eating raw meats, seafood, eggs, or unwashed vegetables when neutropenic due to the risk of acquiring foodborne illnesses. Colony-stimulating factors such as filgrastim (Neupogen) or pegfilgrastim (Neulasta) may be prescribed to prevent or treat neutropenia. These injectable agents stimulate the bone marrow to rapidly produce WBCs, reducing the risk of infection and neutropenic fever. The most common side effects include bone pain, particularly in the long bones, such as the hips and sternum, where bone marrow is produced (Nettina & Nelson-Tuttle, 2024; Norris, 2024; Wingard, 2026).
Anemia. Anemia is a common consequence of chemotherapy and generally becomes more significant with each successive dose due to a cumulative effect as patients progress through treatment. In addition to low hemoglobin and hematocrit, as seen through bloodwork, patients may display pallor, fatigue, low energy, chest pain, shortness of breath, and weakness. Some patients may benefit from oral iron supplementation, folic acid, and an iron-rich diet. Others may require erythropoietin-stimulating agents such as epoetin alfa (Procrit, Epogen) or darbepoetin alfa (Aranesp) or blood transfusions (Nettina & Nelson-Tuttle, 2024; Norris, 2024).
Thrombocytopenia. Thrombocytopenia is a consequence of chemotherapy that heightens the risk of bleeding. Platelets impede bleeding by clumping and forming plaques in blood vessel injuries, such as cuts, lacerations, and other wounds. The risk of bleeding is present when a patient’s platelet count falls below 50,000/mm3, high risk if their count falls below 20,000/mm3, and critical risk if their count falls below 10,000/mm3. Patients may require a platelet transfusion if their count drops below 20,000/mm3. This is particularly dangerous in patients on anticoagulation therapy, as their risk of bleeding is already increased. Signs of thrombocytopenia may include bruising, petechiae, epistaxis, gum bleeding, hematuria, or rectal bleeding. HCPs should counsel patients on strategies to prevent injury, such as avoiding shaving with razors, rectal suppositories, dental floss, or participating in activities that place them at risk for injury (e.g., contact sports, skiing, and horseback riding; Gao et al., 2023; Nettina & Nelson-Tuttle, 2024; Norris, 2024).
Chemotherapy-induced Peripheral Neuropathy (CIPN). CIPN is a common side effect of many types of chemotherapy used to treat pancreatic cancer, such as cisplatin (Platinol), albumin-bound paclitaxel (Abraxane), and oxaliplatin (Eloxatin). CIPN results from the demyelination of sensory and motor axons. Patients experience reduced nerve conduction velocity, leading to the loss of deep tendon reflexes and paresthesia (numbness and tingling), weakness, and burning pain. Initially, CIPN often affects the body’s most distal points, such as the fingertips and toes, progressing proximally toward the midline. In severe cases, patients may lose all sensation in the fingers, hands, toes, and feet; this can cause significant disability, such as the inability to grasp or hold items, and gait disturbance, including imbalance and falls. CIPN is a complex topic since no single pathophysiologic process explains the neuropathies following chemotherapy exposure. CIPN is dose-dependent and progressive while a patient is receiving treatment. Pain, sensory changes, and weakness that manifest during treatment generally lead to chemotherapy dose reductions, changes in treatment protocols, or complete termination of the therapeutic agent. CIPN can also have a cascading effect after treatment ends, whereby symptoms become more prominent after discontinuing the offending agent. CIPN is challenging to manage as it does not respond well to conventional treatments. OTC analgesics, menthol creams, capsaicin creams, or lidocaine patches may offer comfort, but most are ineffective. Gabapentin (Neurontin), an anticonvulsant/anti-epileptic agent, has demonstrated limited efficacy but may cause intolerable side effects of weight gain, depression, sedation, and heightened suicide risk. Some patients may find relief from selective serotonin-norepinephrine reuptake inhibitors (SNRIs) such as duloxetine (Cymbalta). HCPs should counsel patients on strategies to avoid injury (e.g., wearing supportive shoes) and promote home safety (e.g., using handrails on stairs and removing throw rugs). Patients must be mindful of water temperatures due to decreased sensitivity to hot water, increasing their risk for burns when bathing or washing dishes. Improvement in function and resolution of symptoms often occurs gradually over time, but nerve damage may be permanent (Desforges et al., 2022; Lustberg, 2026; Nettina & Nelson-Tuttle, 2024; Norris, 2024).
Targeted Therapy
Poly ADP-Ribose Polymerase Inhibitors
The poly ADP-ribose polymerase (PARP) enzyme serves a critical role in cell growth, cell regulation, and the repair of healthy cells and cancer cells. It fixes DNA damage in cancer cells, helping them repair themselves and survive. PARP inhibitors interfere with the PARP enzyme, preventing cancer cells with a BRCA1/2 mutation from repairing DNA damage and inducing cell death. PARP inhibitors have transformed the treatment of BRCA-mutant cancers. On December 27, 2019, the US Food and Drug Administration (FDA) approved olaparib (Lynparza) for maintenance treatment in patients with germline BRCA1/2 mutations following platinum-based chemotherapy (i.e., cisplatin [Platinol] or oxaliplatin [Eloxatin]). Currently, olaparib (Lynparza) is the only PARP inhibitor approved for use in pancreatic cancer; however, other PARPs such as rucaparib (Rubraca) and niraparib (Zejula) are under clinical investigation, both demonstrating safety and effectiveness in Phase II trials. Olaparib (Lynparza) is administered at 300 mg PO twice daily. The most common side effects include anemia, neutropenia, fatigue, nausea, diarrhea or constipation, anorexia, and arthralgias. They are also associated with a rare risk (under 1.5%) of myelodysplastic syndrome (a bone marrow failure disorder) or acute myeloid leukemia (a type of blood cancer). They carry a slight risk (under 1%) of pneumonitis and embryo-fetal toxicity. PARP inhibitors have several significant drug interactions, particularly with antifungal medications and certain antibiotics. Patients should avoid grapefruit and Seville oranges, as they can increase PARP inhibitors’ effects and toxicity (Ahn et al., 2024; Cardin & Singh, 2026; NCCN, 2026b).
RAS Inhibitor
In August 2026, the FDA approved the first RAS inhibitor targeted therapy for metastatic pancreatic cancer. Daraxonrasib (Rasonque) is an oral tablet taken once daily that targets multiple forms of the RAS protein, which arises in the cells lining the ducts of the pancreas. Daraxonrasib (Rasonque) is approved for adults with metastatic pancreatic adenocarcinoma who have received at least one prior systemic therapy or who are not candidates for multiagent systemic therapy. In an open-label, multicenter clinical trial with previously treated metastatic pancreatic adenocarcinoma, daraxonrasib (Rasonque) improved median overall survival from 6.7 to 13.2 months. The most common side effects include diarrhea, nausea, vomiting, fatigue, abdominal pain, edema, hemorrhage, decreased appetite, rash, and stomatitis (inflammation of the oral mucus membranes; FDA, 2026a).
Immunotherapy
Pembrolizumab (Keytruda)
Immunotherapy is a novel cancer treatment group that stimulates the immune system to recognize and destroy cancer cells. Immunotherapy aims to produce antitumor effects by modifying the actions of the body’s natural host defense mechanisms to become more sensitive to cancer cells. Immune-based treatments work differently from chemotherapy as they are highly specialized in their activity. Immunotherapy’s role in treating pancreatic cancer is less advanced than in other diseases, and clinical research is ongoing. Pembrolizumab (Keytruda) is an immune-based agent currently approved for use in pancreatic cancers. It is FDA-approved for metastatic pancreatic tumors that are MSI-H or dMMR. Pembrolizumab (Keytruda) is a humanized monoclonal antibody that binds with high affinity to the programmed cell death-1 (PD-1)/PD-ligand 1 (PD-L1). PD-1 is a transmembrane checkpoint protein expressed on the surface of circulating immune cells. PD-1 normally acts as an “off switch” to keep the immune cells from attacking other cells in the body. When PD-1 binds to PD-L1, it signals the T-cell to leave the neighboring cells alone. Some cancer cells have large amounts of PD-L1, which helps them evade immune attacks. PD-1 and PD-L1 inhibitors have been designed to prevent the formation of this complex and enable immune cells to continue attacking tumor cells. Drugs targeting PD-1 or PD-L1 are designed to block this binding and boost the immune response against cancer cells. In clinical trials, pembrolizumab (Keytruda) demonstrated promising and durable antitumor activity in patients with PD-L1-positive pancreatic cancer, offering a clinically meaningful and viable treatment strategy (ACS, 2024b; Cardin & Singh, 2026; NCCN, 2026b; Overman & Morse, 2026; Pancreatic Cancer Action Network, n.d.-c).
While pembrolizumab (Keytruda) is typically well-tolerated, all immunotherapy drugs carry boxed warnings for immune-mediated adverse reactions (irAEs), which can be fatal if left untreated. An autoimmune response can impact any organ system, inducing nonspecific inflammation throughout the body. The most common immune-mediated complications include enterocolitis, hepatitis, endocrinopathies (inflammation of the thyroid and adrenal glands), nephritis, and uveitis. Care of the patient receiving immunotherapy requires cautious triage and meticulous assessment to identify signs of potential irAEs. Most irAEs are reversible but require timely intervention with immunosuppressive treatment, typically in the form of corticosteroids. Patient education regarding the importance of self-assessment and immediately reporting symptoms is vital. With pneumonitis, symptoms can range from mild cough and dyspnea to severe shortness of breath and life-threatening hypoxia. GI effects can range from mild diarrhea and abdominal cramping to severe colitis, which can be fatal if not managed. Skin toxicity may present initially as mild pruritus or dermatitis and can progress to Stevens-Johnson syndrome (SJS). SJS is characterized by a painful systemic red rash that leads to blistering and sloughing of the skin’s top layer. Life-threatening endocrinopathies can cause varied symptoms, such as extreme weakness, excessive fatigue or lethargy, electrolyte disturbances, thyroid inflammation, and pituitary dysfunction (ACS, 2024b; Cardin & Singh, 2026; NCCN, 2026b; Overman & Morse, 2026; Pancreatic Cancer Action Network, n.d.-c).
Dostarlimab (Jemperli) is a PD-1-blocking monoclonal antibody that is FDA-approved to treat patients with advanced pancreatic cancer with dMMR. The most common side effects of dostarlimab (Jemperli) include anemia, diarrhea, nausea, and fatigue. Regular laboratory monitoring of liver enzymes, thyroid function, and creatinine levels is required due to the risk of severe irAEs (ACS, 2024b; Cardin & Singh, 2026; O'Hara, n.d.; Overman & Morse, 2026; Pancreatic Cancer Action Network, n.d.-c).
Antitumor Therapy for Functioning PNETs
Aside from surgical excision and chemotherapy, directed treatment strategies are recommended to control the unique hormonal effects of PNETs. The NCCN recommends managing gastric hypersecretion caused by gastrinoma tumors with antisecretory medications, such as proton pump inhibitors (omeprazole [Prilosec], pantoprazole [Protonix], and lansoprazole [Prevacid]). These medications effectively suppress acid secretion, reducing gastric distress, burning, and diarrhea. Somatostatin analogs such as octreotide (Sandostatin) and lanreotide (Somatuline Depot) are synthetic versions of somatostatin that suppress and decelerate hormone production. These injectable agents are primarily administered to palliate symptoms. However, clinical trials have demonstrated the antitumor effects of octreotide (Sandostatin) and lanreotide (Somatuline Depot) in advanced PNETs, suggesting they also help control the disease. The most common adverse reactions include abdominal pain, musculoskeletal pain, muscle spasms, nausea, vomiting, headache, injection site reactions, hyperglycemia, hypertension, and cholelithiasis (ACS, 2025b; Chan et al., 2026; NCCN, 2026b).
Everolimus (Afinitor) is a relatively novel oral agent that inhibits the mammalian target of the rapamycin (mTOR) pathway. The mTOR pathway is a component of a complex intracellular signaling mechanism that serves as a critical regulator of cell physiology in various cancers. Linked to multiple cellular and physiological functions involved in cellular growth, proliferation, and survival, mTOR is used as a drug target in several types of cancers. Initially approved for use in advanced breast cancer, everolimus (Afinitor) has demonstrated efficacy in delaying disease progression of PNETs, controlling symptoms, and preserving the quality of life. The most frequent side effect is oral mucositis, inflammation, irritation, swelling, and ulceration of the oral mucosa and lips. These symptoms can develop as early as 2 weeks after starting the medication. HCPs should educate patients on oral hygiene practices to preserve the oral mucosa’s integrity, such as using soft-bristled toothbrushes and avoiding irritating alcohol-based mouthwashes. Additional reported side effects of everolimus (Afinitor) include fatigue, anorexia, skin rash, diarrhea, and increased serum cholesterol levels. It carries a risk for pneumonitis, impaired wound healing, renal failure, and embryo-fetal toxicity. Everolimus (Afinitor) is also associated with a risk for angioedema in patients taking concomitant angiotensin-converting enzyme inhibitors (ACS, 2025g; Chan et al., 2026; FDA, 2018; NCCN, 2026b).
For an enhanced understanding of chemotherapy, immunotherapy, and targeted cancer treatments, refer to the following NursingCE courses:
- Oncology Prescribing for APRNs
- Oncology Nursing Part 2: Chemotherapy and Oncologic Emergencies
Palliative Care and Pancreatic Cancer
While palliative care should be a standard component of all aspects of cancer care, it is of utmost importance for patients with pancreatic cancer, given the disease’s dismal survival rates and high morbidity. The World Health Organization (WHO, 2020) defines “palliative care” as follows:
an approach that improves the quality of life of patients and their families facing the problem associated with life-threatening illness, through the prevention and relief of suffering by means of early identification and impeccable assessment and treatment of pain and other problems, physical, psychosocial, and spiritual (WHO, 2020, para. 1).
Palliative care is an interdisciplinary medical subspecialty that focuses on alleviating the pain, stressors, and other symptoms associated with serious illness. While the term is widely utilized throughout health care settings, it is often misunderstood. Many confuse palliative care with end-of-life (EOL) and hospice care. The need for palliative care is heightened at the EOL due to increased symptom burden; however, it is appropriate at any point during a chronic illness. Unlike hospice care, palliative care can and should be implemented simultaneously while treating the disease and ideally should be employed throughout the illness trajectory. Palliative care does not intend to hasten or postpone death but offers a support system to help patients live as actively as possible until death. It is based on the patient’s need, not prognosis, and the primary goal is to promote comfort and ease suffering (Fernandez-del Castillo et al., 2025; Meier & McCormick, 2026; Teoli et al., 2023; WHO, 2020).
The Nurse’s Role in Palliative Care
Goals-of-care discussions and advance care planning (ACP) are essential components of palliative care at all stages of illness but become increasingly urgent as the patient’s health status declines. When patients are adequately informed about their diagnosis and prognosis, their choices regarding cardiopulmonary resuscitation (CPR) and additional life-sustaining measures at the EOL are more realistic. Despite popular misconceptions, EOL discussions do not cause emotional harm to patients and their families. When EOL care is discussed, bereaved families report higher satisfaction with the care team’s communication and increased comfort of their loved ones. Patients who have EOL discussions with their care team are more likely to accept their diagnosis as terminal, have an advance directive, and opt for medical treatments focused on relieving pain rather than extending their lives with futile interventions. They are less likely to receive mechanical ventilation, have a feeding tube, undergo resuscitation, or be admitted to an intensive care unit. They are more likely to choose hospice care, which is consistently linked to improved quality of life at the EOL, enhanced symptom control, increased emotional support, and more comfort through the dying process. Hospice is also associated with decreased major depression in bereaved caregivers. Caregivers of patients who received aggressive care in the last weeks of life are more likely to develop a major depressive disorder, experience regret, feel unprepared for the patient’s death, and report poorer quality of life (Fernandez-del Castillo et al., 2025; Meier & McCormick, 2026; Teoli et al., 2023).
Nurses practice at the forefront of primary care across clinical settings. They are well positioned to serve critical roles as palliative care team members and facilitate these open, honest conversations with patients and families. They are responsible for addressing psychological responses, emotions, or changes in cognition as prognosis and care goals evolve during the illness’s trajectory. Nurses advocate for the patient’s dignity and self-esteem by providing palliative care interventions to promote comfort and reduce suffering. They serve fundamental roles in ensuring symptoms are managed throughout the cancer continuum, connecting patients to necessary resources, and implementing measures to preserve the quality of life. Nurses bridge communication between team and family members, so they must acquire practical communication skills to navigate these conversations. Nurses are critical in educating patients and families about these vital decisions, explaining options, and ensuring decisions are aligned with the patient’s goals of care (Fernandez-del Castillo et al., 2025; Meier & McCormick, 2026; Nettina & Nelson-Tuttle, 2024; Teoli et al., 2023).
For additional information regarding palliative care and care at the EOL, refer to the following NursingCE courses:
- End-of-Life Care (with Ethical Issues)
- Palliative Care for APRNs
- Pain Management for APRNs (3-part series)
References
Ahn, E. R., Rothe, M., Mangat, P. K., Garrett-Mayer, E., Calfa, C. J., Alva, A. S., Suhag, V., Alese, O. B., Dotan, E., Hamid, O., Yang, E. S., Marr, A. S., Palmer, M. C., Thompson, F. L., Yost, K. J., Gregory, A., Grantham, G. N., Hinshaw, D. C., Halabi, S., & Schilsky, R. L. (2024). Olaparib in patients with pancreatic cancer with BRCA1/2 mutations: Results from the targeted agent and profiling utilization registry study. JCO Precision Oncology: An American Society of Clinical Oncology Journal, 8, e2300240. https://doi.org/10.1200/PO.23.00240
American Board of Internal Medicine. (2026). ABIM laboratory test reference ranges—January 2026. https://www.abim.org/media/e2wdwdqu/laboratory-reference-ranges.pdf
American Cancer Society. (2024a). Ataxia-telangiectasia (A-T). https://www.cancer.org/cancer/risk-prevention/genetics/family-cancer-syndromes/ataxia.html
American Cancer Society. (2024b). Immunotherapy for pancreatic cancer. https://www.cancer.org/cancer/types/pancreatic-cancer/treating/immunotherapy.html
American Cancer Society. (2024c). Lynch syndrome. https://www.cancer.org/cancer/risk-prevention/genetics/family-cancer-syndromes/lynch-syndrome.html
American Cancer Society. (2024d). Pancreatic cancer stages. https://www.cancer.org/cancer/types/pancreatic-cancer/detection-diagnosis-staging/staging.html
American Cancer Society. (2024e). Signs and symptoms of pancreatic cancer. https://www.cancer.org/cancer/pancreatic-cancer/detection-diagnosis-staging/signs-and-symptoms.html
American Cancer Society. (2025a). Chemotherapy side effects. https://www.cancer.org/cancer/treatment-types/chemotherapy/chemotherapy-side-effects.html
American Cancer Society. (2025b). Drugs used to treat pancreatic neuroendocrine tumor (pNET) symptoms. https://www.cancer.org/cancer/types/pancreatic-neuroendocrine-tumor/treating/other-drugs.html
American Cancer Society. (2025c). Familial adenomatous polyposis (FAP). https://www.cancer.org/cancer/risk-prevention/genetics/family-cancer-syndromes/familial-adenomatous-polyposis.html
American Cancer Society. (2025d). Pancreatic cancer risk factors. https://www.cancer.org/cancer/pancreatic-cancer/causes-risks-prevention/risk-factors.html
American Cancer Society. (2025e). Peutz-Jerghers syndrome (PJS). https://www.cancer.org/cancer/risk-prevention/genetics/family-cancer-syndromes/peutz-jeghers-syndrome.html
American Cancer Society. (2025f). Radiation therapy side effects. https://www.cancer.org/treatment/treatments-and-side-effects/treatment-types/radiation/effects-on-different-parts-of-body.html
American Cancer Society. (2025g). Targeted drug therapy for pancreatic neuroendocrine tumors (pNET). https://www.cancer.org/cancer/types/pancreatic-neuroendocrine-tumor/treating/targeted-therapy.html
American Cancer Society. (2026a). Key statistics for pancreatic cancer. https://www.cancer.org/cancer/pancreatic-cancer/about/key-statistics.html
American Cancer Society. (2026b). Survival rates for pancreatic cancer. https://www.cancer.org/cancer/pancreatic-cancer/detection-diagnosis-staging/survival-rates.html
Amin, M. B., Greene, F. L., Edge, S. B., Compton, C. C., Gershenwald, J. E., Brookland, R. K., Meyer, L., Gress, D. M., Byrd, D. R., & Winchester, D. P. (2017). The eighth edition AJCC cancer staging manual: Continuing to build a bridge from a population-based to a more “personalized” approach to cancer staging. CA: A Cancer Journal for Clinicians, 67(2), 93–99. https://doi.org/10.3322/caac.21388
Bannoura, S. F., Uddin, H., Nagasaka, M., Fazili, F., Al-Hallak, M. N., Philip, P. A., El-Rayes, B., & Azmi, A. S. (2021). Targeting KRAS in pancreatic cancer: New drugs on the horizon. Cancer Metastasis Reviews, 40(3), 819–835. https://doi.org/10.1007/s10555-021-09990-2
Burkon, P., Trna, J., Slavik, M., Nemecek, R., Kazda, T., Pospisil, P., Sastych, M., Eid, M., Novotny, I., Prochazka, T., & Vrzal, M. (2022). Stereotactic body radiotherapy (SBRT) of pancreatic cancer: A critical review and practical consideration. Biomedicines, 10(10), 2480. https://doi.org/10.3390/biomedicines10102480
Cabebe, E. C. (2026a). Pancreatic cancer overview. https://emedicine.medscape.com/article/280605-overview#showall
Cabebe, E. C. (2026b). Pancreatic cancer treatment and management. https://emedicine.medscape.com/article/280605-treatment#showall
Cabebe, E. C. (2026c). Pancreatic cancer workup. https://emedicine.medscape.com/article/280605-workup#showall
Canto, M. I. (2026). Familial risk factors for pancreatic cancer and screening of high-risk patients. UpToDate. Retrieved August 23, 2026, from https://www.uptodate.com/contents/familial-risk-factors-for-pancreatic-cancer-and-screening-of-high-risk-patients
Cardin, D. B., & Singh, H. (2026). Initial systemic therapy for metastatic exocrine pancreatic cancer. UpToDate. Retrieved August 23, 2026, from https://www.uptodate.com/contents/initial-systemic-therapy-for-metastatic-exocrine-pancreatic-cancer
Casale, J., & Patel, P. (2024). Fluorouracil. In StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK549808
Centers for Disease Control and Prevention. (2025). People at increased risk for BRCA gene mutations. https://www.cdc.gov/breast-ovarian-cancer-hereditary/risk-factors/index.html
Centers for Disease Control and Prevention. (2026). Genetic testing for Lynch syndrome. https://www.cdc.gov/colorectal-cancer-hereditary/testing
Chan, J. A., Kulke, M., & Clancy, T. E. (2026). Systemic therapy for locally advanced and metastatic well-differentiated low-grade (G1) and intermediate-grade (G2) pancreatic neuroendocrine tumors. UpToDate. Retrieved August 25, 2026, from https://www.uptodate.com/contents/systemic-therapy-for-locally-advanced-and-metastatic-well-differentiated-low-grade-g1-and-intermediate-grade-g2-pancreatic-neuroendocrine-tumors
Chung, D. C., & Rodgers-Fouche, L. H. (2026). Gene test interpretation: STK11 (Peutz-Jeghers syndrome gene). UpToDate. Retrieved August 23, 2026, from https://www.uptodate.com/contents/gene-test-interpretation-stk11-peutz-jeghers-syndrome-gene
Desforges, A. D., Hebert, C. M., Spence, A. L., Reid, B., Dhaibar, H. A., Cruz-Topete, D., Cornett, E. M., Kaye, A. D., Urits, I., & Viswanath, O. (2022). Treatment and diagnosis of chemotherapy-induced peripheral neuropathy: An update. Biomedicine & Pharmacotherapy, 147, 112671. https://doi.org/10.1016/j.biopha.2022.112671
Fernandez-del Castillo, C., & Jimenez, R. E. (2026a). Epidemiology and nonfamilial risk factors for exocrine pancreatic cancer. UpToDate. Retrieved August 19, 2026, from https://www.uptodate.com/contents/epidemiology-and-nonfamilial-risk-factors-for-exocrine-pancreatic-cancer
Fernandez-del Castillo, C., & Jimenez, R. E. (2026b). Overview of surgery in the treatment of exocrine pancreatic cancer and prognosis. UpToDate. Retrieved August 24, 2026, from https://www.uptodate.com/contents/overview-of-surgery-in-the-treatment-of-exocrine-pancreatic-cancer-and-prognosis
Fernandez-del Castillo, C., Jimenez, R. E., & Murphy, J. E. (2025). Supportive care for locally advanced or metastatic exocrine pancreatic cancer. UpToDate. Retrieved August 25, 2026, from https://www.uptodate.com/contents/supportive-care-for-locally-advanced-or-metastatic-exocrine-pancreatic-cancer
Fernandez-del Castillo, C., & Singh, H. (2026). Clinical presentation, diagnosis, and staging of exocrine pancreatic cancer. UpToDate. Retrieved August 24, 2026, from https://www.uptodate.com/contents/clinical-presentation-diagnosis-and-staging-of-exocrine-pancreatic-cancer
Gao, A., Zhang, L., & Zhong, D. (2023). Chemotherapy-induced thrombocytopenia: Literature review. Discover Oncology, 14(1), 10. https://doi.org/10.1007/s12672-023-00616-3
Genetic and Rare Diseases Information Center. (2026). Familial atypical multiple mole melanoma syndrome. https://rarediseases.info.nih.gov/diseases/9281/fammm-syndrome#ref_13155
Goggins, M., Overbeek, K. A., Brand, R., Syngal, S., Del Chiaro, M., Bartsch, D. K., Bassi, C., Carrato, A., Farrell, J., Fishman, E. K., Fockens, P., Gress, T. M., van Hooft, J., Hruban, R. H., Kastrinos, F., Klein, A., Lennon, A. M., Lucas, A., Park, W., … & International Cancer of the Pancreas Screening (CAPS) Consortium. (2020). Management of patients with increased risk for familial pancreatic cancer: Updated recommendations for the International Cancer of the Pancreas Screening (CAPS) Consortium. Gut, 69(1), 7-17. https://doi.org/10.1136/gutjnl-2019-319352
Gress, F. G. (2024). Endoscopic ultrasound in the staging of exocrine pancreatic cancer. UpToDate. Retrieved August 24, 2026, from https://www.uptodate.com/contents/endoscopic-ultrasound-in-the-staging-of-exocrine-pancreatic-cancer
Hall, M. J., & Neumann, C. C. (2025). Lynch syndrome (hereditary nonpolyposis colorectal cancer): Clinical manifestations and diagnosis. UpToDate. Retrieved August 23, 2026, from https://www.uptodate.com/contents/lynch-syndrome-hereditary-nonpolyposis-colorectal-cancer-clinical-manifestations-and-diagnosis
Hines, O. J. (2024). Surgical resection of lesions of the body and tail of the pancreas. UpToDate. Retrieved August 24, 2026, from https://www.uptodate.com/contents/surgical-resection-of-lesions-of-the-body-and-tail-of-the-pancreas
Hinkle, J. L., Cheever, K. H., Overbaugh, K., & Bradley, C. E. (2025). Brunner & Suddarth’s textbook of medical-surgical nursing (16th ed.). Wolters Kluwer.
Hruban, R. H. (2026). Molecular pathogenesis of exocrine pancreatic cancer. UpToDate. Retrieved August 20, 2026, from https://www.uptodate.com/contents/molecular-pathogenesis-of-exocrine-pancreatic-cancer
Lustberg, M. B. (2026). Prevention and treatment of chemotherapy-induced peripheral neuropathy. UpToDate. Retrieved August 25, 2026, from https://www.uptodate.com/contents/prevention-and-treatment-of-chemotherapy-induced-peripheral-neuropathy
Mahon, S. M. (2020). Germline and somatic variants: What is the difference? https://voice.ons.org/news-and-views/germline-and-somatic-mutations-what-is-the-difference
Mahon, S. M. (2025). Genetic disorder reference sheet: CDKN2A/CDK4. ONS Voice. https://www.ons.org/publications-research/voice/news-views/02-2025/genetic-disorder-reference-sheet-cdkn2acdk4
Mamon, H., Cardin, D. B., Singh, H., & Fernandez-del Castillo, C. (2026a). Treatment of locally advanced exocrine pancreatic cancer. UpToDate. Retrieved August 25, 2026, from https://www.uptodate.com/contents/treatment-of-locally-advanced-exocrine-pancreatic-cancer
Mamon, H., Cardin, D. B., Singh, H., & Fernandez-del Castillo, C. (2026b). Treatment of resectable exocrine pancreatic cancer. UpToDate. Retrieved August 24, 2026, from https://www.uptodate.com/contents/treatment-of-resectable-exocrine-pancreatic-cancer
MedlinePlus. (2025). Familial adenomatous polyposis. National Library of Medicine. https://medlineplus.gov/genetics/condition/familial-adenomatous-polyposis
Meier, D. E., & McCormick, E. (2026). Benefits, services, and models of subspecialty palliative care. UpToDate. Retrieved August 25, 2026, from https://www.uptodate.com/contents/benefits-services-and-models-of-subspecialty-palliative-care
National Cancer Institute. (2024). American Joint Committee on Cancer (AJCC). https://training.seer.cancer.gov/staging/systems/ajcc.html
National Cancer Institute. (2025a). Pancreatic cancer treatment (PDQ®)—Health professional version. https://www.cancer.gov/types/pancreatic/hp/pancreatic-treatment-pdq
National Cancer Institute. (2025b). Pancreatic neuroendocrine tumors (islet cell tumors) treatment (PDQ®)—Health professional version. https://www.cancer.gov/types/pancreatic/hp/pnet-treatment-pdq
National Comprehensive Cancer Network. (2026a). NCCN clinical practice guidelines in oncology (NCCN guidelines®): Genetic/familial high-risk assessment: Breast, ovarian, pancreatic, and prostate, version 3.2026. https://www.nccn.org/professionals/physician_gls/pdf/genetics_bopp.pdf
National Comprehensive Cancer Network. (2026b). NCCN clinical practice guidelines in oncology (NCCN guidelines®): Pancreatic adenocarcinoma, version 3.2026. https://www.nccn.org/professionals/physician_gls/pdf/pancreatic.pdf
National Human Genome Research Institute. (2026). Autosomal dominant disorder. National Institute of Health. https://www.genome.gov/genetics-glossary/Autosomal-Dominant-Disorder
Nettina, S. M., & Nelson-Tuttle, C. (2024). Lippincott manual of nursing practice (12th ed.). Wolters Kluwer.
Norris, T. L. (2024). Porth’s pathophysiology: Concepts of altered health states (11th ed.). Wolters Kluwer.
O'Hara, M. (n.d.). What makes immunotherapy for pancreatic cancer a promising treatment? Cancer Research Institute. Retrieved August 25, 2026, from https://www.cancerresearch.org/cancer-types/pancreatic-cancer
ONS Voice. (2024). Oncology drug reference sheet: Oxaliplatin. https://www.ons.org/publications-research/voice/news-views/09-2024/oncology-drug-reference-sheet-oxaliplatin
ONS Voice. (2025). Oncology drug reference sheet: Cisplatin. https://www.ons.org/publications-research/voice/news-views/01-2025/oncology-drug-reference-sheet-cisplatin
Opal, P. (2026). Ataxia-telangiectasia. UpToDate. Retrieved August 23, 2026, from https://www.uptodate.com/contents/ataxia-telangiectasia
Overman, M. J., & Morse, M. (2026). Overview of advanced unresectable and metastatic solid tumors with DNA mismatch repair deficiency or high tumor mutational burden. UpToDate. Retrieved August 25, 2026, from https://www.uptodate.com/contents/overview-of-advanced-unresectable-and-metastatic-solid-tumors-with-dna-mismatch-repair-deficiency-or-high-tumor-mutational-burden
Pancreatic Cancer Action Network. (n.d.-a). Chemotherapy for pancreatic cancer. Retrieved August 25, 2026, from https://pancan.org/facing-pancreatic-cancer/treatment/treatment-types/chemotherapy
Pancreatic Cancer Action Network. (n.d.-b). Endoscopic retrograde cholangiopancreatography (ERCP). Retrieved August 24, 2026, from https://www.pancan.org/facing-pancreatic-cancer/diagnosis/endoscopic-retrograde-cholangiopancreatography-ercp
Pancreatic Cancer Action Network. (n.d.-c). Immunotherapy for pancreatic cancer. Retrieved August 25, 2026, from https://pancan.org/facing-pancreatic-cancer/treatment/treatment-types/immunotherapy
Pancreatic Cancer Action Network. (n.d.-d). Pancreatic cancer genetic mutations. Retrieved August 23, 2026, from https://pancan.org/facing-pancreatic-cancer/about-pancreatic-cancer/risk-factors/genetic-hereditary/genetic-mutations
Pancreatic Cancer Action Network. (n.d.-e). Pancreatic exocrine tumors. Retrieved August 24, 2026, from https://pancan.org/facing-pancreatic-cancer/about-pancreatic-cancer/types-of-pancreatic-cancer/exocrine
Pancreatic Cancer Action Network. (n.d.-f). Radiation therapy for pancreatic cancer. Retrieved August 24, 2026, from https://pancan.org/facing-pancreatic-cancer/treatment/treatment-types/radiation-therapy
Peshkin, B. N., & Isaacs, C. (2026). Overview of hereditary breast, ovarian, pancreatic, and prostatic cancer syndromes. UpToDate. Retrieved August 23, 2026, from https://www.uptodate.com/contents/overview-of-hereditary-breast-ovarian-pancreatic-and-prostatic-cancer-syndromes
Puckett, Y., & Garfield, K. (2024). Pancreatic cancer. In StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK518996
RadiologyInfo.org. (2024a). General ultrasound. https://www.radiologyinfo.org/en/info.cfm?pg=genus
RadiologyInfo.org. (2024b). Pancreatic cancer. https://www.radiologyinfo.org/en/info.cfm?pg=pancreatic-cancer
Reber, H. A. (2025). Surgical resection of lesions of the head of the pancreas. UpToDate. Retrieved August 24, 2026, from https://www.uptodate.com/contents/surgical-resection-of-lesions-of-the-head-of-the-pancreas
Reyhanoglu, G., & Smith, T. (2023). Irinotecan. In StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK554441
Rogers, J. (2022). McCance & Huether’s Pathophysiology: The biologic basis for disease in adults and children (9th ed.). Elsevier.
Schwarzenberg, S. J. (2025). Pancreatitis associated with genetic risk factors: Causes, evaluation, and management. UpToDate. Retrieved August 23, 2026, from https://www.uptodate.com/contents/pancreatitis-associated-with-genetic-risk-factors-causes-evaluation-and-management
Sherman, S., Menon, G., & Krishnamurthy, K. (2025). Peutz-Jeghers syndrome. In StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK535357
Siegel, R. L., Kratzer, T. B., Wagle, N. S., Sung, H., & Jemal, A. (2026). Cancer statistics, 2026. CA: A Cancer Journal for Clinicians, 76(1), e70043. https://doi.org/10.3322/caac.70043
Stefanoudakis, D., Frountzas, M., Schizas, D., Michalopoulos, N. V., Drakaki, A., & Toutouzas, K. G. (2024). Significance of TP53, CDKN2A, SMAD4, and KRAS in pancreatic cancer. Current Issues in Molecular Biology, 46(4), 2827-2844. https://doi.org/10.3390/cimb46040177
Strosberg, J. R. (2026). Clinical presentation, diagnosis, and staging of pancreatic neuroendocrine neoplasms. UpToDate. Retrieved August 24, 2026, from https://www.uptodate.com/contents/clinical-presentation-diagnosis-and-staging-of-pancreatic-neuroendocrine-neoplasms
Suriawinata, A. (2025). Pathology of exocrine pancreatic neoplasms. UpToDate. Retrieved August 24, 2026, from https://www.uptodate.com/contents/pathology-of-exocrine-pancreatic-neoplasms
Surveillance, Epidemiology, and End Results Program. (2026). Cancer stat facts: Pancreatic cancer. National Cancer Institute. https://seer.cancer.gov/statfacts/html/pancreas.html
Talathi, S. S., Omole, A. E., & Young, M. (2025). Anatomy, abdomen and pelvis, pancreas. In StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK532912
Teoli, D., Schoo, C., & Kalish, V. B. (2023). Palliative care. In StatPearls [Internet]. StatPearls Publishing. https://www.ncbi.nlm.nih.gov/books/NBK537113
To, B. A. T. (2024). Peutz-Jeghers syndrome overview. https://emedicine.medscape.com/article/182006-overview
US Food and Drug Administration. (2018). Highlights of prescribing information: Afinitor®(everolimus). https://www.accessdata.fda.gov/drugsatfda_docs/label/2018/022334s040,203985s013lbl.pdf
US Food and Drug Administration. (2019). Highlights of prescribing information: Gemcitabine injection. https://www.accessdata.fda.gov/drugsatfda_docs/label/2019/209604s004lbl.pdf
US Food and Drug Administration. (2026a). FDA approves first in class targeted therapy for metastatic pancreatic cancer. https://www.fda.gov/news-events/press-announcements/fda-approves-first-class-targeted-therapy-metastatic-pancreatic-cancer
US Food and Drug Administration. (2026b). FDA approves first-of-its-kind device to treat pancreatic cancer. https://www.fda.gov/news-events/press-announcements/fda-approves-first-its-kind-device-treat-pancreatic-cancer
US Food and Drug Administration. (2026c). Safety labeling update for capecitabine and fluorouracil (5-FU) on risks associated with dihydropyrimidine dehydrogenase (DPD) deficiency. https://www.fda.gov/drugs/resources-information-approved-drugs/safety-labeling-update-capecitabine-and-fluorouracil-5-fu-risks-associated-dihydropyrimidine
Villano, A. (2025a). Lynch syndrome. https://www.merckmanuals.com/professional/oncology/tumors-of-the-gastrointestinal-tract/lynch-syndrome
Villano, A. (2025b). Pancreatic cancer. https://www.merckmanuals.com/professional/gastrointestinal-disorders/tumors-of-the-gastrointestinal-tract/pancreatic-cancer
Wingard, J. R. (2026). Risk assessment of adults with chemotherapy-induced neutropenia. UpToDate. Retrieved August 25, 2026, from https://www.uptodate.com/contents/risk-assessment-of-adults-with-chemotherapy-induced-neutropenia
World Health Organization. (2020). Palliative care: Key facts. https://www.who.int/news-room/fact-sheets/detail/palliative-care
Yaskin, J. C. (1931). Nervous symptoms as earliest manifestations of carcinoma of the pancreas. JAMA, 96(20), 1664-1668. https://doi.org/10.1001/jama.1931.02720460010003
Zhang, Z., Zhang, H., Liao, X., & Tsai, H. (2023). KRAS mutation: The booster of pancreatic ductal adenocarcinoma transformation and progression. Frontiers in Cell and Developmental Biology, 11, 1147676. https://doi.org/10.3389/fcell.2023.1147676
Powered by Froala Editor